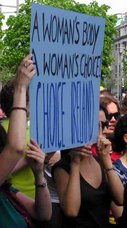Foetus seized in abortion inquiry
John Hooper in Rome
This article appeared in the Guardian on Thursday February 14 2008 on p27 of the International section. It was last updated at 09:28 on February 14 2008.
Police entered a hospital in Naples,interrogated a woman who had just had her pregnancy terminated, andimpounded her aborted foetus after a tip-off from a caller who claimedshe was having the abortion outside the legal time limits.
In aninterview with the paper La Repubblica the woman, known only asSilvana, said: "I didn't understand what was happening. I was stillunder the effects of the anaesthetic. They bombarded me with questions.They gave me the third degree: how did it happen, why did I have anabortion, who was the father?"
In fact, as doctors laterconfirmed, her pregnancy was terminated in its 21st week, which waswithin the period allowed by Italy's 1978 abortion act. The doctorsalso said that tests had shown the foetus had grave abnormalities.
Theincident involving the woman, who said she had wanted the child "at allcosts" and only reluctantly agreed to the termination, comes as thesubject of abortion looks set to play an important role in Italy'sgeneral election in April.
Commenting on the incident in Naples,Livia Turco, the health minister in the outgoing centre-leftgovernment, said: "The witchhunt is on. What happened mirrors theintolerable climate of tension surrounding one of the most dramaticchoices for a woman."
Doctors in Italy can legally performabortions until about the 24th week if the mother's life is at risk orthe foetus is seriously malformed. But critics say the law should bemore restrictive since medical advances make it possible for babiesborn earlier than this to survive.
Giuliano Ferrara, who editsa newspaper supported by Silvio Berlusconi's wife, Veronica Lario, hascalled for the UN to declare a moratorium on abortions, a causeendorsed by Berlusconi himself this week. Like Berlusconi, Ferrara willbe standing for parliament at the general election, but at the head ofan independent, anti-abortion party.
Tuesday, February 19, 2008


Monday, February 18, 2008
Unsafe abortions - The silent pandemic- Jamaica
From Jamaica-Gleaner.com
Unsafe abortions - The silent pandemic
published: Sunday | February 17, 2008
Heather Little-White, Ph.D., Contributor
As advocacy for increased access to safe, legal abortion continues in Jamaica, arguments for or against it are usually well presented. Unplanned or unwanted pregnancies are a reality of life, so Sheronbelieves that abortion should be made legal so that it can be safe for those who need to have one done. Sheron, 38, a victim of unsafe backdoor abortion, tells her story.
"I remember visiting the country at age 20 to visit my ailing grandmother. My grandmother had to be hospitalised and most times I was alone in the house. One day my uncle came home from work early, to my surprise. He always had 'eyes for me' but I used to tell him how disgusted I was with his behaviour. Later that day as I was taking a shower, I heard the bathroom door open, it was my uncle, naked as the day he was born ... he pushed me against the shower, and forced himself on me, raping me despite my pleas to stop. I could not fight him off with my small frame as he was a tall, heavyset man.
"I felt dirty and ashamed. Days later, I eventually found the courage to tell my mother, who did not believe me and accused me of telling lies on her brother. I cried even more. Weeks passed, I missed my period and realised that I was pregnant, I decided that no way could I carry a child for my uncle ... when my mother discovered that was I pregnant, she was alarmed and offered to take me to a 'doctor' in town.
"I remember ascending a flight of stairs to a dusty room where I was asked to lay on a table behind a black curtain. Today the visit is still vivid in my mind. I was given a cup of warn drink and soon felt drowsy. Later, the middle-aged 'doctor' asked me to spread my legs, he pressed my stomach hard, asked me to take a deep breath and I could feel a cold instrument being inserted into my vagina, then a piercing pain, after about an hour or so I was released in pain and blood, the bleeding continued for three days despite the doctor's promise of a couple hours. I realised that I had an abortion which resulted in infections and my inability to conceive later in life and the psychological effect is like a nightmare."
Sheron's story concurs with similar stories from an estimated 20 million women around the world who have unsafe abortions annually (Allan Guttmacher Institute, 1999). However, some victims of unsafe abortion do not live to tell the tale. Anti-abortionists argue that women should not find themselves in the position where they end with unplanned or unwanted pregnancies, even though these may occur for a number of reasons.
Like Sheron, pregnancy could result from incest or rape or from failure to use contraceptive, pressure from a partner not to use contraceptive, contraceptive failure and changes in circumstances that make a pregnancy unwanted, such as abandonment, relationship problems with husband or partner, risks to maternal health and financial difficulties. Women may also want to pursue educational or career goals and will want to postpone childbearing. The number of unplanned pregnancies illustrates the unmet needs of family planning.
Unsanitary conditions
The World Health Organisation (WHO) defines an unsafe abortion as a procedure to terminate an unintended pregnancy by untrained persons who are styled as 'doctors', and usually in unsanitary conditions that do not conform to medical standards. In the United States, a slang term for unsafe abortions is back alley abortions, characterised by the use of a coat hanger. The magnitude of unsafe abortions in the United States led to Roe vs Wade Supreme Court decision 1973 to legalise abortion in America.
In developing countries, unsafe abortion places women at risk because abortion is highly restricted by law, or where it is legally permitted safe abortion is not easily accessible. According to WHO, an estimated 20 million unsafe abortions are performed each year with 95 per cent in developing countries. Simply put, unsafe abortions are performed at a rate of eight per hour.
Bitter concoctions
Unsafe abortion use self-induced methods which are crude, dangerous and even fatal. These include taking teas and herbal remedies, such as boiled avocado or basil leaves, wine boiled with cinnamon and raisins, boiled celery water with aspirin and bitter concoctions; ingesting alcohol and toxic solutions such as turpentine, detergent solutions, bleach and acid; pushing objects into the uterus, such as a stick, wire, coat hanger, knitting needle, ballpoint pen, bicycle spoke, rubber tubing; air blown in the vagina by a syringe and physical damage such as an abdominal or back massage, lifting heavy weight or falling or jumping from the top of stairs or roof when there is no other way to end an unwanted pregnancy. Pharmaceuticals administered include uterine stimulants, such as misoprostol or oxytocin, and quinine or chloroquine used for treating malaria.
On the contrary, safe abortions are performed by trained professionals in sterile conditions using safe methods like pharmaceuticals, suction curettage and induced labour. When performed in sanitary conditions, legal abortions are one of the safest procedures in contemporary medicine. However, the cost of safe abortions is usually prohibitive, which causes poor women to delay getting an abortion until later into the pregnancy when the risk is greater. Regardless of the legal status of abortion, the data show that poor women are at greater risk for undergoing unsafe abortions using primitive, unsafe methods for self-induced abortions.
Bleeding
Morbidity complications resulting from unsafe abortions include incomplete abortion, infection (sepsis), haemorrhage and trauma to the cervix, vagina and uterus and injury to internal organs, such as puncturing or tearing of the uterus. Long- term damage includes chronic pain, pelvic inflammatory disease (PID) and infertility. Death is also a consequence of unsafe, illegal abortions. Globally, WHO estimates that 68,000 women die each year from unsafe abortions. Teenagers comprise a significant proportion of victims of unsafe abortion because they tend to wait to seek abortion later than do older women and are at greater risk of complication.
Abortions conducted in unsafe conditions put the lives of many women at risk and present a grave public health problem to governments. Consensus from the IV World Conference of Women in Beijing 1995, posited that the majority of deaths, injuries and abortion-related health problems could have been prevented with improved access to health services, including safe and effective methods of birth control and gynaecological care.
Public health issue
At the 1994 International Conference on Population and Development (ICPD), nations around the world agreed that societies must ensure high-quality, compassionate treatment for complications resulting from unsafe abortions; provide access to family planning; reform restrictive laws that limit the availability of safe services and trained professionals and ensure safe abortion services. Public health record indicates that safe, legal accessible abortion improves health. The ICPD conference resolved that governments should work to eliminate unsafe abortions by an integrated, comprehensive approach involving health workers, policymakers and advocates.
Name changed for privacy
Unsafe abortions - The silent pandemic
published: Sunday | February 17, 2008
Heather Little-White, Ph.D., Contributor
As advocacy for increased access to safe, legal abortion continues in Jamaica, arguments for or against it are usually well presented. Unplanned or unwanted pregnancies are a reality of life, so Sheronbelieves that abortion should be made legal so that it can be safe for those who need to have one done. Sheron, 38, a victim of unsafe backdoor abortion, tells her story.
"I remember visiting the country at age 20 to visit my ailing grandmother. My grandmother had to be hospitalised and most times I was alone in the house. One day my uncle came home from work early, to my surprise. He always had 'eyes for me' but I used to tell him how disgusted I was with his behaviour. Later that day as I was taking a shower, I heard the bathroom door open, it was my uncle, naked as the day he was born ... he pushed me against the shower, and forced himself on me, raping me despite my pleas to stop. I could not fight him off with my small frame as he was a tall, heavyset man.
"I felt dirty and ashamed. Days later, I eventually found the courage to tell my mother, who did not believe me and accused me of telling lies on her brother. I cried even more. Weeks passed, I missed my period and realised that I was pregnant, I decided that no way could I carry a child for my uncle ... when my mother discovered that was I pregnant, she was alarmed and offered to take me to a 'doctor' in town.
"I remember ascending a flight of stairs to a dusty room where I was asked to lay on a table behind a black curtain. Today the visit is still vivid in my mind. I was given a cup of warn drink and soon felt drowsy. Later, the middle-aged 'doctor' asked me to spread my legs, he pressed my stomach hard, asked me to take a deep breath and I could feel a cold instrument being inserted into my vagina, then a piercing pain, after about an hour or so I was released in pain and blood, the bleeding continued for three days despite the doctor's promise of a couple hours. I realised that I had an abortion which resulted in infections and my inability to conceive later in life and the psychological effect is like a nightmare."
Sheron's story concurs with similar stories from an estimated 20 million women around the world who have unsafe abortions annually (Allan Guttmacher Institute, 1999). However, some victims of unsafe abortion do not live to tell the tale. Anti-abortionists argue that women should not find themselves in the position where they end with unplanned or unwanted pregnancies, even though these may occur for a number of reasons.
Like Sheron, pregnancy could result from incest or rape or from failure to use contraceptive, pressure from a partner not to use contraceptive, contraceptive failure and changes in circumstances that make a pregnancy unwanted, such as abandonment, relationship problems with husband or partner, risks to maternal health and financial difficulties. Women may also want to pursue educational or career goals and will want to postpone childbearing. The number of unplanned pregnancies illustrates the unmet needs of family planning.
Unsanitary conditions
The World Health Organisation (WHO) defines an unsafe abortion as a procedure to terminate an unintended pregnancy by untrained persons who are styled as 'doctors', and usually in unsanitary conditions that do not conform to medical standards. In the United States, a slang term for unsafe abortions is back alley abortions, characterised by the use of a coat hanger. The magnitude of unsafe abortions in the United States led to Roe vs Wade Supreme Court decision 1973 to legalise abortion in America.
In developing countries, unsafe abortion places women at risk because abortion is highly restricted by law, or where it is legally permitted safe abortion is not easily accessible. According to WHO, an estimated 20 million unsafe abortions are performed each year with 95 per cent in developing countries. Simply put, unsafe abortions are performed at a rate of eight per hour.
Bitter concoctions
Unsafe abortion use self-induced methods which are crude, dangerous and even fatal. These include taking teas and herbal remedies, such as boiled avocado or basil leaves, wine boiled with cinnamon and raisins, boiled celery water with aspirin and bitter concoctions; ingesting alcohol and toxic solutions such as turpentine, detergent solutions, bleach and acid; pushing objects into the uterus, such as a stick, wire, coat hanger, knitting needle, ballpoint pen, bicycle spoke, rubber tubing; air blown in the vagina by a syringe and physical damage such as an abdominal or back massage, lifting heavy weight or falling or jumping from the top of stairs or roof when there is no other way to end an unwanted pregnancy. Pharmaceuticals administered include uterine stimulants, such as misoprostol or oxytocin, and quinine or chloroquine used for treating malaria.
On the contrary, safe abortions are performed by trained professionals in sterile conditions using safe methods like pharmaceuticals, suction curettage and induced labour. When performed in sanitary conditions, legal abortions are one of the safest procedures in contemporary medicine. However, the cost of safe abortions is usually prohibitive, which causes poor women to delay getting an abortion until later into the pregnancy when the risk is greater. Regardless of the legal status of abortion, the data show that poor women are at greater risk for undergoing unsafe abortions using primitive, unsafe methods for self-induced abortions.
Bleeding
Morbidity complications resulting from unsafe abortions include incomplete abortion, infection (sepsis), haemorrhage and trauma to the cervix, vagina and uterus and injury to internal organs, such as puncturing or tearing of the uterus. Long- term damage includes chronic pain, pelvic inflammatory disease (PID) and infertility. Death is also a consequence of unsafe, illegal abortions. Globally, WHO estimates that 68,000 women die each year from unsafe abortions. Teenagers comprise a significant proportion of victims of unsafe abortion because they tend to wait to seek abortion later than do older women and are at greater risk of complication.
Abortions conducted in unsafe conditions put the lives of many women at risk and present a grave public health problem to governments. Consensus from the IV World Conference of Women in Beijing 1995, posited that the majority of deaths, injuries and abortion-related health problems could have been prevented with improved access to health services, including safe and effective methods of birth control and gynaecological care.
Public health issue
At the 1994 International Conference on Population and Development (ICPD), nations around the world agreed that societies must ensure high-quality, compassionate treatment for complications resulting from unsafe abortions; provide access to family planning; reform restrictive laws that limit the availability of safe services and trained professionals and ensure safe abortion services. Public health record indicates that safe, legal accessible abortion improves health. The ICPD conference resolved that governments should work to eliminate unsafe abortions by an integrated, comprehensive approach involving health workers, policymakers and advocates.
Name changed for privacy
Abortion Too Easy, Some Spaniards Say
By DANIEL WOOLLS –
MADRID, Spain (AP) — After same-sex marriage and fast-track divorce, Spain's social revolution has hit a roadblock — abortion.
The abortion law, severely restrictive during Gen. Francisco Franco's dictatorship of the predominantly Roman Catholic country, was liberalized in 1985. But abortion has become too easy to obtain, say its opponents, and lately it has flared into a dispute so bitter it prompted abortion clinics to go on strike for five days.
Staffers have been arrested and 25 women who underwent abortions have been interrogated. At one point thousands of women swarmed a Madrid courthouse, shouting that they too had terminated a pregnancy, and demanding a change in the law to provide abortion on demand.
At issue is a crackdown on five facilities accused of performing abortions in violation of the law that permits them in the first 12 weeks in case of rape, 22 weeks in case of fetal malformation, and at any time if a psychiatrist certifies that the mother's physical or mental health is endangered.
Politically, it's a delicate matter. The Socialists, seeking re-election March 9, have quietly dropped a pledge of abortion on demand up to 12 or 14 weeks into a pregnancy, as exists in many other European countries, for fear of alienating centrist voters. The opposition conservatives, also seeking centrist support, are shying away from promising a complete ban as their allies in the church demand.
But for some, Spain's abortion law is already much too liberal. "In Spain, it is harder to cut down a tree illegally than it is to commit an abortion," Josep Miro i Ardevol, who leads a group called e-Cristians, wrote on its Web site.
The trouble began when police raided and shut private abortion clinics in Barcelona and Madrid in November and December, acting on complaints from church-affiliated groups that the facilities were carrying out illegal abortions.
One prominent clinic owner in Barcelona was among 13 people arrested, and he spent two months in jail until his release in mid-January. Two others remain in custody, although no one has been formally charged.
The Association of Accredited Abortion Clinics says the police searches were aggressive while demonstrators harassed patients and employees with threatening phone calls and graffiti such as "Murder is committed here."
It said that after authorities didn't respond to its pleas for protection, it called the Jan. 8-12 strike, shutting down around 40 clinics and forcing the postponement of nearly 2,000 procedures. "We are absolutely desperate because this is no way to work," Empar Pineda, the association's spokeswoman, said in an interview.
Around 100,000 abortions were carried out in 2006 in Spain, which has a population of 45 million. In Italy, by comparison, with a population of 58 million, the figure is about 137,000 for 2004, the last year for which full figures are available.
In Spain women who have an abortion can get the government to pay for it, but nationwide around 60 percent pay for it themselves, mainly because this way it is faster and more confidential. All the clinics under investigation are privately owned.
More than 90 percent of Spain's abortions fell into the category of women citing mental distress, said Pineda.
The complaints that prompted the raids were filed by e-Cristians, which alleges a gross lack of government supervision and record-keeping.
No charges have been formally brought, but the Barcelona clinics are suspected of using bogus psychiatric certificates, according to an official with the Civil Guard, which made the arrests. The two people who remain in custody are psychiatrists, the official said, speaking on condition of anonymity because of department rules.
Pineda acknowledged that the mental-distress argument is a loophole, "a bit of theater that we play out" because Spain doesn't have abortion on demand. Under Franco, the only grounds for an abortion was a "family honor" clause designed to spare parents the embarrassment of an unwed daughter having a baby, Pineda said.
In the case of the Madrid raids, Pineda blamed the harassment on conservatives who run the regional government. Its president, Esperanza Aguirre, is seen as a candidate to take over her Popular Party's national leadership if it loses the March election, and "is winking at her electorate to show that she is tough," Pineda said.
The ruling Socialist Party, meanwhile, has already infuriated conservatives and the Roman Catholic church with its sweeping reforms and having once promised abortion on demand, now says it is open to a "period of reflection."
MADRID, Spain (AP) — After same-sex marriage and fast-track divorce, Spain's social revolution has hit a roadblock — abortion.
The abortion law, severely restrictive during Gen. Francisco Franco's dictatorship of the predominantly Roman Catholic country, was liberalized in 1985. But abortion has become too easy to obtain, say its opponents, and lately it has flared into a dispute so bitter it prompted abortion clinics to go on strike for five days.
Staffers have been arrested and 25 women who underwent abortions have been interrogated. At one point thousands of women swarmed a Madrid courthouse, shouting that they too had terminated a pregnancy, and demanding a change in the law to provide abortion on demand.
At issue is a crackdown on five facilities accused of performing abortions in violation of the law that permits them in the first 12 weeks in case of rape, 22 weeks in case of fetal malformation, and at any time if a psychiatrist certifies that the mother's physical or mental health is endangered.
Politically, it's a delicate matter. The Socialists, seeking re-election March 9, have quietly dropped a pledge of abortion on demand up to 12 or 14 weeks into a pregnancy, as exists in many other European countries, for fear of alienating centrist voters. The opposition conservatives, also seeking centrist support, are shying away from promising a complete ban as their allies in the church demand.
But for some, Spain's abortion law is already much too liberal. "In Spain, it is harder to cut down a tree illegally than it is to commit an abortion," Josep Miro i Ardevol, who leads a group called e-Cristians, wrote on its Web site.
The trouble began when police raided and shut private abortion clinics in Barcelona and Madrid in November and December, acting on complaints from church-affiliated groups that the facilities were carrying out illegal abortions.
One prominent clinic owner in Barcelona was among 13 people arrested, and he spent two months in jail until his release in mid-January. Two others remain in custody, although no one has been formally charged.
The Association of Accredited Abortion Clinics says the police searches were aggressive while demonstrators harassed patients and employees with threatening phone calls and graffiti such as "Murder is committed here."
It said that after authorities didn't respond to its pleas for protection, it called the Jan. 8-12 strike, shutting down around 40 clinics and forcing the postponement of nearly 2,000 procedures. "We are absolutely desperate because this is no way to work," Empar Pineda, the association's spokeswoman, said in an interview.
Around 100,000 abortions were carried out in 2006 in Spain, which has a population of 45 million. In Italy, by comparison, with a population of 58 million, the figure is about 137,000 for 2004, the last year for which full figures are available.
In Spain women who have an abortion can get the government to pay for it, but nationwide around 60 percent pay for it themselves, mainly because this way it is faster and more confidential. All the clinics under investigation are privately owned.
More than 90 percent of Spain's abortions fell into the category of women citing mental distress, said Pineda.
The complaints that prompted the raids were filed by e-Cristians, which alleges a gross lack of government supervision and record-keeping.
No charges have been formally brought, but the Barcelona clinics are suspected of using bogus psychiatric certificates, according to an official with the Civil Guard, which made the arrests. The two people who remain in custody are psychiatrists, the official said, speaking on condition of anonymity because of department rules.
Pineda acknowledged that the mental-distress argument is a loophole, "a bit of theater that we play out" because Spain doesn't have abortion on demand. Under Franco, the only grounds for an abortion was a "family honor" clause designed to spare parents the embarrassment of an unwed daughter having a baby, Pineda said.
In the case of the Madrid raids, Pineda blamed the harassment on conservatives who run the regional government. Its president, Esperanza Aguirre, is seen as a candidate to take over her Popular Party's national leadership if it loses the March election, and "is winking at her electorate to show that she is tough," Pineda said.
The ruling Socialist Party, meanwhile, has already infuriated conservatives and the Roman Catholic church with its sweeping reforms and having once promised abortion on demand, now says it is open to a "period of reflection."
Saturday, February 16, 2008
Italians Rally to Defend Abortion Law
ROME (AP) — Hundreds of women rallied in Rome and Naples on Thursday to protest police interrogation of a woman after she underwent an abortion and to oppose a campaign push by some conservatives to change Italy's abortion law.
State television said at least one woman was detained by police after protesters scuffled with officers when they tried to move the rally to a square in central Rome.
Health Minister Livia Turco emerged from her office earlier in a show of solidarity with demonstrators, who held placards proclaiming that "Women do the choosing" and other slogans.
Turco has denounced an incident earlier in the week when police rushed into a Naples hospital to interrogate a woman who had aborted a 21-week-old fetus minutes before. The 39-year-old woman says she had the abortion after learning the fetus had a grave genetic defect. News reports said the aborted fetus was seized as evidence.
The police investigation came amid a drive seeking to limit the point in a pregnancy when abortion should be allowed. Proponents of limits claim medical advances mean 21-week fetuses can sometimes survive.
Abortion after three months is allowed in Italy when a pregnancy is deemed a grave danger to a woman's mental or physical health.
Abortion through the end of the third month of any pregnancy was legalized in 1978, and three years later Italians voted to keep the law despite opposition from the Vatican.
But abortion has become an issue in the campaign for parliamentary elections April 13-14.
Conservative former premier Silvio Berlusconi says he wants the United Nations to approve a worldwide moratorium on abortions. Newspaper editor Giuliano Ferrara sharpened the debate by announcing he will run for Parliament on an anti-abortion platform.
Berlusconi's opponent for the premiership, center-left candidate Walter Veltroni, was quoted by the Italian news agency Apcom on Thursday as defending Italy's abortion law. He cited statistics showing a drop in abortions since 1978 and said the law also "wiped out the plague of clandestine abortions which caused so many deaths among women."
State television said at least one woman was detained by police after protesters scuffled with officers when they tried to move the rally to a square in central Rome.
Health Minister Livia Turco emerged from her office earlier in a show of solidarity with demonstrators, who held placards proclaiming that "Women do the choosing" and other slogans.
Turco has denounced an incident earlier in the week when police rushed into a Naples hospital to interrogate a woman who had aborted a 21-week-old fetus minutes before. The 39-year-old woman says she had the abortion after learning the fetus had a grave genetic defect. News reports said the aborted fetus was seized as evidence.
The police investigation came amid a drive seeking to limit the point in a pregnancy when abortion should be allowed. Proponents of limits claim medical advances mean 21-week fetuses can sometimes survive.
Abortion after three months is allowed in Italy when a pregnancy is deemed a grave danger to a woman's mental or physical health.
Abortion through the end of the third month of any pregnancy was legalized in 1978, and three years later Italians voted to keep the law despite opposition from the Vatican.
But abortion has become an issue in the campaign for parliamentary elections April 13-14.
Conservative former premier Silvio Berlusconi says he wants the United Nations to approve a worldwide moratorium on abortions. Newspaper editor Giuliano Ferrara sharpened the debate by announcing he will run for Parliament on an anti-abortion platform.
Berlusconi's opponent for the premiership, center-left candidate Walter Veltroni, was quoted by the Italian news agency Apcom on Thursday as defending Italy's abortion law. He cited statistics showing a drop in abortions since 1978 and said the law also "wiped out the plague of clandestine abortions which caused so many deaths among women."
Abortion Law Is Suddenly a Pivotal Issue in Italy’s Elections
by ELISABETTA POVOLEDO
Published: February 16, 2008
ROME — With voting less than two months away, a bitter debate over abortion has unexpectedly flared up, putting the issue at the center of the Italian electoral campaign.
The controversy over Italy’s 30-year-old law legalizing abortion stirred up demonstrations this week in its defense, with Health Minister Livia Turco among the protesters.
The demonstrations were touched off by an incident in a Naples hospital on Monday.
Acting on an anonymous tip that an abortion had been performed later in a pregnancy than the law allows, police officers entered the hospital and interrogated a Neapolitan woman, identified in the news media only by her first name, Silvana, immediately after the abortion and reportedly while she was still under the effects of anesthesia. They seized the aborted fetus.
Carmine Nappi, the chief of obstetrics at the hospital, likened the police intrusion to an anti-Mafia raid. “We’ve had countless complaints, we’re a hospital, but never a blitz like this,” he said by telephone on Thursday.
On Thursday evening, protesters gathered in several Italian cities. In Rome, a few hundred women and some men, many holding signs that read, “Silvana, we’re all with you,” stopped traffic in front of the Health Ministry. Ms. Turco praised the turnout. “We’re defending a law that is close to us,” she said.
On Friday, a group of women staged a sit-in in front of the Naples hospital.
An internal investigation at the hospital determined that the woman, 39, had terminated her pregnancy during the 21st week, within the 24-week limit set by the law, after tests disclosed that the fetus could have significant abnormalities.
In mid-December, Giuliano Ferrara, a conservative journalist close to former Prime Minister Silvio Berlusconi, the center-right leader, began using his daily newspaper, Il Foglio, as a platform to support a universal moratorium on abortion. This week, he announced that he would run for Parliament as an independent in the April 13-14 elections on an anti-abortion ticket.
Critics of Mr. Ferrara’s campaign have accused him of trying to create fractures within the newly formed center-left Democratic Party, which has a sizable Roman Catholic component.
Center-left leaders have rejected calls to overturn the abortion law, which was upheld in a 1981 referendum after a battle with Italy’s Catholic establishment.
The law also includes provisions for family planning clinics and counseling for young women to avoid unplanned pregnancies. Many point to Health Ministry statistics to underscore the law’s effectiveness: In 2006, there were 130,000 terminated pregnancies in Italy, 44.6 percent fewer than in 1982, when 234,801 abortions were carried out.
Polls indicate that Mr. Berlusconi’s coalition will probably be the winner in the parliamentary elections, and some legislators allied with him are already calling for changes in the abortion law.
Published: February 16, 2008
ROME — With voting less than two months away, a bitter debate over abortion has unexpectedly flared up, putting the issue at the center of the Italian electoral campaign.
The controversy over Italy’s 30-year-old law legalizing abortion stirred up demonstrations this week in its defense, with Health Minister Livia Turco among the protesters.
The demonstrations were touched off by an incident in a Naples hospital on Monday.
Acting on an anonymous tip that an abortion had been performed later in a pregnancy than the law allows, police officers entered the hospital and interrogated a Neapolitan woman, identified in the news media only by her first name, Silvana, immediately after the abortion and reportedly while she was still under the effects of anesthesia. They seized the aborted fetus.
Carmine Nappi, the chief of obstetrics at the hospital, likened the police intrusion to an anti-Mafia raid. “We’ve had countless complaints, we’re a hospital, but never a blitz like this,” he said by telephone on Thursday.
On Thursday evening, protesters gathered in several Italian cities. In Rome, a few hundred women and some men, many holding signs that read, “Silvana, we’re all with you,” stopped traffic in front of the Health Ministry. Ms. Turco praised the turnout. “We’re defending a law that is close to us,” she said.
On Friday, a group of women staged a sit-in in front of the Naples hospital.
An internal investigation at the hospital determined that the woman, 39, had terminated her pregnancy during the 21st week, within the 24-week limit set by the law, after tests disclosed that the fetus could have significant abnormalities.
In mid-December, Giuliano Ferrara, a conservative journalist close to former Prime Minister Silvio Berlusconi, the center-right leader, began using his daily newspaper, Il Foglio, as a platform to support a universal moratorium on abortion. This week, he announced that he would run for Parliament as an independent in the April 13-14 elections on an anti-abortion ticket.
Critics of Mr. Ferrara’s campaign have accused him of trying to create fractures within the newly formed center-left Democratic Party, which has a sizable Roman Catholic component.
Center-left leaders have rejected calls to overturn the abortion law, which was upheld in a 1981 referendum after a battle with Italy’s Catholic establishment.
The law also includes provisions for family planning clinics and counseling for young women to avoid unplanned pregnancies. Many point to Health Ministry statistics to underscore the law’s effectiveness: In 2006, there were 130,000 terminated pregnancies in Italy, 44.6 percent fewer than in 1982, when 234,801 abortions were carried out.
Polls indicate that Mr. Berlusconi’s coalition will probably be the winner in the parliamentary elections, and some legislators allied with him are already calling for changes in the abortion law.
Friday, February 08, 2008
Feminists and Unions present 4000 self-accusations of abortion at Court
Feminists and unions present 4,000 self-accusations of abortion at Court
Madrid, February 8, 2008.- Representatives of more than 72 feminist and family planning organizations and unions have presented 4,000 self-accusations of abortion at the Court in Madrid yesterday, in the context of the “For women’s right to choose” campaign.
The move follows the aim of being supportive with those women who have been required to state in Court as well as demanding changes in the current legislation of abortion in Spain.
At present, the interruption of pregnancy is considered a crime under the Penal Code, the reason why all these organizations have demanded an urgent change of this consideration.
Some background on the abortion issue in Spain
In Spain, abortion is illegal except when a woman has been raped (the termination must be done in the first 12 weeks of pregnancy), in the case of foetal malformations (up to 22 weeks’ gestation), and when the woman faces grave danger to her life or physical or mental health (there is no time limit in this case).
At present almost all abortions are carried out in private clinics, as the public health system covers only 2.5 percent of the total. This "weakness" in state healthcare is heavily influenced by the Catholic Church’s anti-abortion campaign, according to family support organisations.
Health Ministry statistics indicate that the number of abortions in the country has doubled in the last decade.
Every year, one woman out of 100 in the age range of 15 to 44 has an abortion. Of these, 40 percent are under 25 and 14 percent are under 19 years old.
The rise in the number of abortions performed in Spain should be countered with education for children and young people, and not with crackdowns, the head of the Women’s Forum in Madrid’s city government, Lourdes Hernández, told IPS last January.
Guillermo González, head of the FPFE, agreed with Hernández about the need for sex education, "which is practically non-existent." Sex education should be part of the official school curriculum, "although not necessarily as a separate subject," he told IPS.
An issue which should be speedily addressed, he said, is the sale of contraceptives, "which should be available over-the counter, as it is unacceptable that only condoms can be purchased without a prescription."
"The first item to be deregulated should be the morning-after pill (emergency contraception), which has proven to have very few side-effects, and is an important aid for women to make their own decision about whether or not to become pregnant, as is their prerogative," he said.
Spain’s legislation on abortion is the most restrictive in Europe, while Dutch laws are the most liberal. Women in the Netherlands can have an abortion on demand at any time up to 24 weeks’ gestation.
Medical sources in Spain point out that the time limit of 22 weeks for malformed foetuses means that if malformations incompatible with survival are discovered after that gestational age, an abortion cannot be performed and the woman must give birth to a baby who is doomed to die.
The Association of Accredited Abortion Clinics (ACAI), which represents about 50 private clinics, is calling for a law to allow women to make a free choice about whether or not to remain pregnant, "with no interference from the state," within the first 12 weeks of gestation. Only from the 13th week would conditions and limitations be set for the termination of pregnancy.
In response to anti-abortion declarations and physical attacks on abortion clinics by campaigners, González said that "the sectors that are against sex education, contraceptives and the morning-after pill are the same ones that later clutch their heads because abortions are rising."
"What they really want is for no one to have sex, but that isn’t going to happen, so the only solution is to provide information and birth control," he said.
Family planning organisations calling for the decriminalisation of abortion, and the Catholic Church and its followers demanding the opposite, will have to wait until the new parliament convenes after the Mar. 9 elections, as the previous parliament’s sessions have ended.
The statement presented at Court
The text released by these organizations to support their own “For women’s right to choose” which was handed out at the Court, says:
“The feminist and family planning organizations and unions organizing the ‘For women’s right to choose’ campaign, present at the Court in Madrid some 4,000 self-accusations collected at Madrid.
“2,478 women have stated having interrupted their pregnancies voluntarily and responsibly; 1,422 men and women have stated having supported a woman in her abortion.
“These signatures presented in Madrid are added to those other signatures collected in other cities of other Autonomous Communities, such as Granada, Jaén, Cádiz, Vigo, León, Burgos, Salamanca, Segovia, Zaragoza, and Barcelona. Already, some 1,072 signatures were presented in Asturias, some 280 in Valladolid, some 139 in Córdoba; next February, 14 more signatures will be presented in Granada and next February, 16 in Cantabria. Today, more signatures will be presented in Valencia.
“With the presentation of these self-accusations, all these organizations want to be supportive with those women who have been required to state at the Courts 35 and 47 of the city of Madrid, in a move that is part of the push of conservative groups whose goal is to hinder the women’s right to abortion; we also assume the consequences following these statements, demanding to be required to state in Court if necessary; with our statement, we want to report the situation of social and legal vulnerability facing those women who decide to abort and those medical professionals who attend such choices.
“We consider that this situation takes place as a result of the inadequacies of the current partial decriminalisation of abortion. This is why we demand an immediate change of the current legislation: a) That abortion is no longer considered as a crime under the Penal Code; b) The guarantee of the practice of abortion in the public health system; c) The respect of women’s right to choose.
“We call for a mobilization in view of next March, 8 a date who celebrates the Woman’s International Day, to keep on stating our demands.
“Groups supporting the “For Women’s Right to Choose” Campaign:
ACSURAS
Asamblea Feminista de Madrid
Asociación de Asistencia a Mujeres Violadas
Asociación de Mujeres de la Enseñanza
Asociación de Mujeres Juristas Themis
Asociación de Mujeres para la Salud
Asociación de Mujeres Progresistas "Plaza Mayor”
Asociación de Mujeres Viva la Pepa
Asociación de Planificación Familiar de Madrid
Asociación Igualadas Madrid
Asociación Lasexologia.
Católicas por el Derecho a Decidir
CEM. Centro de Estudios de la Mujer
Colectivo en defensa de los derechos de las prostitutas. Hetaira
Colectivo LILAS
Comisión para la Investigación de Malos Tratos a Mujeres
Consejo de la Mujer del Municipio de Madrid
Coordinadora de Asociaciones de Carabanchel
Coordinadora Española del Lobby Europeo de Mujeres
Enclave Feminista
Eskalera Karakola
Federación de Planificación Familiar Estatal - FPFE
Federación de Asociaciones de Mujeres Separadas y Divorciadas
Federación de Mujeres Progresistas
Federación Mujeres Jóvenes
Forum de Política Feminista
Fundación Mujeres
Genera & Enlaces: Coalición Asociativa
Grupo de Interés Español en Población, Desarrollo y Salud Reproductiva – Grupo GIE
Grupo de Buenos Tratos de Liberación – Amauta
Grupo de Mujeres de Carabanchel
Grupo de Mujeres de Comillas
Grupo de Mujeres de Vallecas
Grupo de Mujeres feministas de Espacio Alternativo
Las Federicas Tejiendo Salud
Organización de Mujeres de STERM-Intersindical
Mujeres de Negro de Madrid
Mujeres en Red
Mujeres en Rojo
Mujeres Vecinales de Madrid
Nosotras Mismas de Chamberí
Nosotras No Nos Resignamos
Partido Feminista
Plataforma de Mujeres 2000
RQTR. Asoc. de lesbianas, gays, transexuales y bisexuales de la Univ. Complutense
Secretaría de la Mujer de CCOO de Madrid. Secretaría Confederal de la Mujer de COO
Secretaría de Igualdad de UGT-Madrid
STEM (Sindicato de Trabajadoras de la Enseñanza de Madrid)
Asociación de mujeres “Las Tejedoras”
Asociación de mujeres de Alcorcón
Asociación Mujeres en Marcha
Asociación de Mujeres de las Artes Escénicas Marías Guerreras
Asociación de Mujeres en lucha contra los malos tratos de Rivas-Vaciamadrid
Asociación Mujeres Opañel.
Asociación Nosotras en el Mundo
Centro de estudios de la Mujer de Las Rozas
Colectivo de jóvenas feministas
Colectivo de Mujeres Convboca
Consejo de la Mujer de la Comunidad de Madrid
LiberACCIÓN - LGTB de izquierdas
Mujeres vecinales de Villa Rosa.
Asociación de Mujeres La Pasionaria (Rivas-Vaciamadrid)
Area de mujer de la asociación Cultura y Cooperación al Desarrollo (CUCO)
AMASOL Asociación de Madres Solas, Familias Monoparentales
Área de la Mujer de Radio Vallekas
AsOciación de Mujeres por un Envejecimiento Saludable.
Asociación Solidaridad con Madres Solteras
Mujeres por la Salud y la Paz.
Plataforma de Mujeres Artistas contra la Violencia de Género
Red Internacional de Mujeres Periodistas y Comunicadoras – Madrid
Secretaría de la Mujer de la Unión de Actores de Madrid
Área de la Mujer. Asociación libre de abogados (ALA)
Equipo de Género de la Asociación AESCO (América-España Solidaridad y Cooperación)
Mujeres de Socialismo Libertario”.
Madrid, February 8, 2008.- Representatives of more than 72 feminist and family planning organizations and unions have presented 4,000 self-accusations of abortion at the Court in Madrid yesterday, in the context of the “For women’s right to choose” campaign.
The move follows the aim of being supportive with those women who have been required to state in Court as well as demanding changes in the current legislation of abortion in Spain.
At present, the interruption of pregnancy is considered a crime under the Penal Code, the reason why all these organizations have demanded an urgent change of this consideration.
Some background on the abortion issue in Spain
In Spain, abortion is illegal except when a woman has been raped (the termination must be done in the first 12 weeks of pregnancy), in the case of foetal malformations (up to 22 weeks’ gestation), and when the woman faces grave danger to her life or physical or mental health (there is no time limit in this case).
At present almost all abortions are carried out in private clinics, as the public health system covers only 2.5 percent of the total. This "weakness" in state healthcare is heavily influenced by the Catholic Church’s anti-abortion campaign, according to family support organisations.
Health Ministry statistics indicate that the number of abortions in the country has doubled in the last decade.
Every year, one woman out of 100 in the age range of 15 to 44 has an abortion. Of these, 40 percent are under 25 and 14 percent are under 19 years old.
The rise in the number of abortions performed in Spain should be countered with education for children and young people, and not with crackdowns, the head of the Women’s Forum in Madrid’s city government, Lourdes Hernández, told IPS last January.
Guillermo González, head of the FPFE, agreed with Hernández about the need for sex education, "which is practically non-existent." Sex education should be part of the official school curriculum, "although not necessarily as a separate subject," he told IPS.
An issue which should be speedily addressed, he said, is the sale of contraceptives, "which should be available over-the counter, as it is unacceptable that only condoms can be purchased without a prescription."
"The first item to be deregulated should be the morning-after pill (emergency contraception), which has proven to have very few side-effects, and is an important aid for women to make their own decision about whether or not to become pregnant, as is their prerogative," he said.
Spain’s legislation on abortion is the most restrictive in Europe, while Dutch laws are the most liberal. Women in the Netherlands can have an abortion on demand at any time up to 24 weeks’ gestation.
Medical sources in Spain point out that the time limit of 22 weeks for malformed foetuses means that if malformations incompatible with survival are discovered after that gestational age, an abortion cannot be performed and the woman must give birth to a baby who is doomed to die.
The Association of Accredited Abortion Clinics (ACAI), which represents about 50 private clinics, is calling for a law to allow women to make a free choice about whether or not to remain pregnant, "with no interference from the state," within the first 12 weeks of gestation. Only from the 13th week would conditions and limitations be set for the termination of pregnancy.
In response to anti-abortion declarations and physical attacks on abortion clinics by campaigners, González said that "the sectors that are against sex education, contraceptives and the morning-after pill are the same ones that later clutch their heads because abortions are rising."
"What they really want is for no one to have sex, but that isn’t going to happen, so the only solution is to provide information and birth control," he said.
Family planning organisations calling for the decriminalisation of abortion, and the Catholic Church and its followers demanding the opposite, will have to wait until the new parliament convenes after the Mar. 9 elections, as the previous parliament’s sessions have ended.
The statement presented at Court
The text released by these organizations to support their own “For women’s right to choose” which was handed out at the Court, says:
“The feminist and family planning organizations and unions organizing the ‘For women’s right to choose’ campaign, present at the Court in Madrid some 4,000 self-accusations collected at Madrid.
“2,478 women have stated having interrupted their pregnancies voluntarily and responsibly; 1,422 men and women have stated having supported a woman in her abortion.
“These signatures presented in Madrid are added to those other signatures collected in other cities of other Autonomous Communities, such as Granada, Jaén, Cádiz, Vigo, León, Burgos, Salamanca, Segovia, Zaragoza, and Barcelona. Already, some 1,072 signatures were presented in Asturias, some 280 in Valladolid, some 139 in Córdoba; next February, 14 more signatures will be presented in Granada and next February, 16 in Cantabria. Today, more signatures will be presented in Valencia.
“With the presentation of these self-accusations, all these organizations want to be supportive with those women who have been required to state at the Courts 35 and 47 of the city of Madrid, in a move that is part of the push of conservative groups whose goal is to hinder the women’s right to abortion; we also assume the consequences following these statements, demanding to be required to state in Court if necessary; with our statement, we want to report the situation of social and legal vulnerability facing those women who decide to abort and those medical professionals who attend such choices.
“We consider that this situation takes place as a result of the inadequacies of the current partial decriminalisation of abortion. This is why we demand an immediate change of the current legislation: a) That abortion is no longer considered as a crime under the Penal Code; b) The guarantee of the practice of abortion in the public health system; c) The respect of women’s right to choose.
“We call for a mobilization in view of next March, 8 a date who celebrates the Woman’s International Day, to keep on stating our demands.
“Groups supporting the “For Women’s Right to Choose” Campaign:
ACSURAS
Asamblea Feminista de Madrid
Asociación de Asistencia a Mujeres Violadas
Asociación de Mujeres de la Enseñanza
Asociación de Mujeres Juristas Themis
Asociación de Mujeres para la Salud
Asociación de Mujeres Progresistas "Plaza Mayor”
Asociación de Mujeres Viva la Pepa
Asociación de Planificación Familiar de Madrid
Asociación Igualadas Madrid
Asociación Lasexologia.
Católicas por el Derecho a Decidir
CEM. Centro de Estudios de la Mujer
Colectivo en defensa de los derechos de las prostitutas. Hetaira
Colectivo LILAS
Comisión para la Investigación de Malos Tratos a Mujeres
Consejo de la Mujer del Municipio de Madrid
Coordinadora de Asociaciones de Carabanchel
Coordinadora Española del Lobby Europeo de Mujeres
Enclave Feminista
Eskalera Karakola
Federación de Planificación Familiar Estatal - FPFE
Federación de Asociaciones de Mujeres Separadas y Divorciadas
Federación de Mujeres Progresistas
Federación Mujeres Jóvenes
Forum de Política Feminista
Fundación Mujeres
Genera & Enlaces: Coalición Asociativa
Grupo de Interés Español en Población, Desarrollo y Salud Reproductiva – Grupo GIE
Grupo de Buenos Tratos de Liberación – Amauta
Grupo de Mujeres de Carabanchel
Grupo de Mujeres de Comillas
Grupo de Mujeres de Vallecas
Grupo de Mujeres feministas de Espacio Alternativo
Las Federicas Tejiendo Salud
Organización de Mujeres de STERM-Intersindical
Mujeres de Negro de Madrid
Mujeres en Red
Mujeres en Rojo
Mujeres Vecinales de Madrid
Nosotras Mismas de Chamberí
Nosotras No Nos Resignamos
Partido Feminista
Plataforma de Mujeres 2000
RQTR. Asoc. de lesbianas, gays, transexuales y bisexuales de la Univ. Complutense
Secretaría de la Mujer de CCOO de Madrid. Secretaría Confederal de la Mujer de COO
Secretaría de Igualdad de UGT-Madrid
STEM (Sindicato de Trabajadoras de la Enseñanza de Madrid)
Asociación de mujeres “Las Tejedoras”
Asociación de mujeres de Alcorcón
Asociación Mujeres en Marcha
Asociación de Mujeres de las Artes Escénicas Marías Guerreras
Asociación de Mujeres en lucha contra los malos tratos de Rivas-Vaciamadrid
Asociación Mujeres Opañel.
Asociación Nosotras en el Mundo
Centro de estudios de la Mujer de Las Rozas
Colectivo de jóvenas feministas
Colectivo de Mujeres Convboca
Consejo de la Mujer de la Comunidad de Madrid
LiberACCIÓN - LGTB de izquierdas
Mujeres vecinales de Villa Rosa.
Asociación de Mujeres La Pasionaria (Rivas-Vaciamadrid)
Area de mujer de la asociación Cultura y Cooperación al Desarrollo (CUCO)
AMASOL Asociación de Madres Solas, Familias Monoparentales
Área de la Mujer de Radio Vallekas
AsOciación de Mujeres por un Envejecimiento Saludable.
Asociación Solidaridad con Madres Solteras
Mujeres por la Salud y la Paz.
Plataforma de Mujeres Artistas contra la Violencia de Género
Red Internacional de Mujeres Periodistas y Comunicadoras – Madrid
Secretaría de la Mujer de la Unión de Actores de Madrid
Área de la Mujer. Asociación libre de abogados (ALA)
Equipo de Género de la Asociación AESCO (América-España Solidaridad y Cooperación)
Mujeres de Socialismo Libertario”.
Over 400 pro-choice supporters at London protest
Last night, more than 400 loud and enthusiastic pro-choice supporters protested outside Central Hall Westminster against the London leg of an anti-abortion road show with Ann Widdecombe MP and Lord David Alton.
The lively crowd, including pro-choice activists, students, trade unionists, and others, brought banners and placards, and raised their voices demanding 'our bodies, our lives, our right to decide' 'not the church, not the state, women must decide their fate' and 'hey, ho, attack our rights? We say no!'
and could be heard across at Parliament. Colourful placards read '83 per cent support choice', 'no attack on the time limit - defend a woman's right to choose' and 'more abortion rights, not less!'.
The protest showed the strength feeling in support of a woman's right to choose on abortion and against any planned attacks on women's abortion rights in Parliament by anti-abortion MPs in coming months - particularly on the abortion time limit. The road show with Ann Widdecombe aims to mobilise anti-abortionists to lobby MPs ahead of key votes.
The wide range of support expressed for the protest included Christine McCafferty MP, Emily Thornberry MP, Fiona McTaggart MP; Baroness Joyce Gould, Baroness Jenny Tonge, Katherine Rake, Director Fawcett Society; Anni Marjoram, Advisor to Mayor of London; Jane Loftus, CWU President; Siobhan Endean, Women's Officer UNITE the UNION; Sharon Green UNISON; Megan Dobney, Secretary SERTUC; Kat Stark NUS Women's Officer;.
The protest follows a huge public meeting called by Abortion Rights in Parliament on 16th February to launch the pro-choice campaigning around the HFE Bill. The meeting attracted so many, that supporters queued around the building to get in and speakers from all three main parties rotated between overspill rooms to address the crowds.
Abortion Rights will be calling public initiatives at every key stage of the Human Fertilisation and Embryology Bill. Further protests are planned are being organised for Liverpool on 12th February, Coventry on 13th February and Cardiff on 4th March 2008. The next mobilisation in London will be for International Women's Day on 8th March. The will be a mass lobby of parliament and other activities at later stages of the Bill. Details to be announced at www.abortionrights.org.uk
Christine McCafferty MP said:
We heavily defeated Nadine Dorries MP's backbench Bill to lower the abortion time limit last year. I led the opposition. I spoke and I voted against it and I am determined that any similar amendments to the Human Fertilisation and Embryology Bill must be defeated again. In the 40th anniversary year of the enactment of the 1967 Abortion Act, we cannot allow the tiny minority who oppose all abortion to chip away women's fundamental rights. Women's rights should be extended not restricted.
Baroness Jenny Tonge In the next few weeks amendments to the Human Fertilization and Embryology Bill will be tabled by abortion opponents in the House of Commons. The House of Lords rejected the one amendment tabled on abortion for foetal disability by 4 to 1. This was very encouraging because there had been heavy lobbying by groups opposing abortion. All of you here today must lobby your MP to make sure that he or she knows that women must retain the right to choose whether or not they continue with a pregnancy. This is the most important issue. We must not let them dilute the
1967 Act in any way.
Katherine Rake Director Fawcett Society Today, women across the UK are celebrating the anniversary of a momentous historical event. On this day ninety years ago women won the right to vote.
It is ironic that this very day, women are having to meet to organise in defence of another hard-won right: the right for women to make decisions about their own bodies.
The Fawcett Society fully supports Abortion Rights' Pro-choice Campaign. The further restrictions which are being proposed to women's access to abortion would be a regression of women's fundamental rights.
The right to an abortion is vital in itself. But there are also clear links between women's reproductive rights and broader equality between women and men - a woman's right to choose is linked to her ability to make economic choices, choices about partnerhips, and choices about her own health.
Women campaigned for the vote, and for the right to abortion, so that they would be able to have control over decisions which affected their lives. We must continue fighting to ensure that these rights are built upon, not eroded, in the coming years.
Louise Hutchins Abortion Rights Campaign Coordinator said:
Abortion Rights is determined that all anti-abortion amendments moved as part of the Human Fertilisation and Embryology Bill currently in Parliament are defeated, and that any opportunity to advance the abortion law for women is maximised. We are protesting as a positive public expression of the strength feeling of the pro-choice majority and of opposition to organised attacks on women's fundamental rights.
The lively crowd, including pro-choice activists, students, trade unionists, and others, brought banners and placards, and raised their voices demanding 'our bodies, our lives, our right to decide' 'not the church, not the state, women must decide their fate' and 'hey, ho, attack our rights? We say no!'
and could be heard across at Parliament. Colourful placards read '83 per cent support choice', 'no attack on the time limit - defend a woman's right to choose' and 'more abortion rights, not less!'.
The protest showed the strength feeling in support of a woman's right to choose on abortion and against any planned attacks on women's abortion rights in Parliament by anti-abortion MPs in coming months - particularly on the abortion time limit. The road show with Ann Widdecombe aims to mobilise anti-abortionists to lobby MPs ahead of key votes.
The wide range of support expressed for the protest included Christine McCafferty MP, Emily Thornberry MP, Fiona McTaggart MP; Baroness Joyce Gould, Baroness Jenny Tonge, Katherine Rake, Director Fawcett Society; Anni Marjoram, Advisor to Mayor of London; Jane Loftus, CWU President; Siobhan Endean, Women's Officer UNITE the UNION; Sharon Green UNISON; Megan Dobney, Secretary SERTUC; Kat Stark NUS Women's Officer;.
The protest follows a huge public meeting called by Abortion Rights in Parliament on 16th February to launch the pro-choice campaigning around the HFE Bill. The meeting attracted so many, that supporters queued around the building to get in and speakers from all three main parties rotated between overspill rooms to address the crowds.
Abortion Rights will be calling public initiatives at every key stage of the Human Fertilisation and Embryology Bill. Further protests are planned are being organised for Liverpool on 12th February, Coventry on 13th February and Cardiff on 4th March 2008. The next mobilisation in London will be for International Women's Day on 8th March. The will be a mass lobby of parliament and other activities at later stages of the Bill. Details to be announced at www.abortionrights.org.uk
Christine McCafferty MP said:
We heavily defeated Nadine Dorries MP's backbench Bill to lower the abortion time limit last year. I led the opposition. I spoke and I voted against it and I am determined that any similar amendments to the Human Fertilisation and Embryology Bill must be defeated again. In the 40th anniversary year of the enactment of the 1967 Abortion Act, we cannot allow the tiny minority who oppose all abortion to chip away women's fundamental rights. Women's rights should be extended not restricted.
Baroness Jenny Tonge In the next few weeks amendments to the Human Fertilization and Embryology Bill will be tabled by abortion opponents in the House of Commons. The House of Lords rejected the one amendment tabled on abortion for foetal disability by 4 to 1. This was very encouraging because there had been heavy lobbying by groups opposing abortion. All of you here today must lobby your MP to make sure that he or she knows that women must retain the right to choose whether or not they continue with a pregnancy. This is the most important issue. We must not let them dilute the
1967 Act in any way.
Katherine Rake Director Fawcett Society Today, women across the UK are celebrating the anniversary of a momentous historical event. On this day ninety years ago women won the right to vote.
It is ironic that this very day, women are having to meet to organise in defence of another hard-won right: the right for women to make decisions about their own bodies.
The Fawcett Society fully supports Abortion Rights' Pro-choice Campaign. The further restrictions which are being proposed to women's access to abortion would be a regression of women's fundamental rights.
The right to an abortion is vital in itself. But there are also clear links between women's reproductive rights and broader equality between women and men - a woman's right to choose is linked to her ability to make economic choices, choices about partnerhips, and choices about her own health.
Women campaigned for the vote, and for the right to abortion, so that they would be able to have control over decisions which affected their lives. We must continue fighting to ensure that these rights are built upon, not eroded, in the coming years.
Louise Hutchins Abortion Rights Campaign Coordinator said:
Abortion Rights is determined that all anti-abortion amendments moved as part of the Human Fertilisation and Embryology Bill currently in Parliament are defeated, and that any opportunity to advance the abortion law for women is maximised. We are protesting as a positive public expression of the strength feeling of the pro-choice majority and of opposition to organised attacks on women's fundamental rights.
Wednesday, January 30, 2008
A Canadian Controversy- A Wise and Just Decision, Worthy of Canadians
A Canadian controversy
A wise and just decision, worthy of Canadians
Laura Wershler
For The Calgary Herald
Monday, January 28, 2008
As Canadians celebrate, agitate or ruminate on the 20th anniversary of the Supreme Court decision to strike down Canada's abortion laws, it is time to consider the general impact of this judgment.
Twenty years without any abortion law is considered scandalous by some. Yet, when compared to other countries with laws governing abortion, Canada is an intriguing example of how unnecessary such laws actually may be.
Writing in a National Post commentary on Jan. 22, 2008, David Frum called the Canadian situation "the Western world's most radical abortion regime." In this case, radical is best defined as going to the root or foundation of something. Radical as in fundamental.
The fundamental truth of having no abortion laws (and universal health care) is that positive outcomes have ensued. When comparing the U.S. situation to ours, a reasonable thinking person would admit that having no law has been more effective at managing outcomes than has the morass of restrictions legislated south of the border.
Canadian women, proportionally, have almost one-third fewer abortions than American women. In Canada, more abortions are done by 12 weeks than in the U.S. Canada also has one of the lowest maternal mortality and complication rates for abortion in the world.
In addition, Canada's abortion rates are similar to or lower than those in European countries that do have laws restricting abortion and have generally been in decline since 1997.
What the Morgentaler decision has meant for Canada is that abortion has settled into the domain in which it rightly belongs -- the health-care system. It is a medical procedure that, as two decades have proved, can be appropriately regulated by provincial Colleges of Physicians and Surgeons.
Canada's abortion statistics bear this out, including those related to the most controversial aspect of our no-law status -- that there are no legal restrictions on late-term abortions.
Procedures occurring after 20 weeks gestation make up less than 0.4 percent of abortions. Late-term abortion is rare, difficult to access and provided only in cases of serious maternal or fetal health problems.
It is inflammatory to suggest as does a recent national billboard campaign by LifeCanada that women do or can access abortion on demand when they are nine months pregnant.
To further demonstrate how abortion laws have no real power to impact actual abortion rates, consider a study by the Guttmacher Institute and the World Health Organization published in October 2007 by the journal Lancet.
It found that abortion rates in countries worldwide are similar regardless of whether the procedure is legal or not. "The legal status of abortion has never dissuaded women and couples, who, for whatever reason, seek to end pregnancy," said Beth Fredrick of the International Women's Health Coalition commenting on the study.
Herein lies another fundamental truth about abortion. That whether legal or not, safe or not, abortion is a choice often made by normal women all around the world. We cannot deny this. We could do worse as a society than to normalize abortion as a fact of human experience. Not normal as in blase, but normal as in standard, natural, common.
Canada, it could be argued, has been doing just this for the past 20 years. We have, to a lesser or greater degree, depending on where you live in this expansive country, normalized abortion as a medically necessary, reasonably accessible and compassionately delivered health-care procedure.
Canada also continues striving, through sexual health education and services, to reduce the need for abortion.
Perhaps this normalization is what most aggravates those who want to keep the abortion controversy simmering -- or boiling over onto the political stovetop.
Barbara Kay, also writing in the National Post last week, argued that Canadians who believe abortion should be restricted in some cases have been silenced. She noted astutely that "the 20-year anniversary of any transformative social decision is a good moment for a dispassionate review of the decision's consequences."
Could it be the consequences that have kept our politicians from responding to calls for discussion on legal restrictions to abortion?
After all, a dispassionate review reveals that abortion in Canada is being appropriately regulated by the medical profession with reasonable outcomes equal to or better than countries that do have laws restricting abortion.
All things considered, it appears the decision made 20 years ago today by the Supreme Court of Canada was wise, just and worthy of Canadians.
Laura Wershler is a sexual health advocate, writer and speaker. She is the executive director of Sexual Health Access Alberta
A wise and just decision, worthy of Canadians
Laura Wershler
For The Calgary Herald
Monday, January 28, 2008
As Canadians celebrate, agitate or ruminate on the 20th anniversary of the Supreme Court decision to strike down Canada's abortion laws, it is time to consider the general impact of this judgment.
Twenty years without any abortion law is considered scandalous by some. Yet, when compared to other countries with laws governing abortion, Canada is an intriguing example of how unnecessary such laws actually may be.
Writing in a National Post commentary on Jan. 22, 2008, David Frum called the Canadian situation "the Western world's most radical abortion regime." In this case, radical is best defined as going to the root or foundation of something. Radical as in fundamental.
The fundamental truth of having no abortion laws (and universal health care) is that positive outcomes have ensued. When comparing the U.S. situation to ours, a reasonable thinking person would admit that having no law has been more effective at managing outcomes than has the morass of restrictions legislated south of the border.
Canadian women, proportionally, have almost one-third fewer abortions than American women. In Canada, more abortions are done by 12 weeks than in the U.S. Canada also has one of the lowest maternal mortality and complication rates for abortion in the world.
In addition, Canada's abortion rates are similar to or lower than those in European countries that do have laws restricting abortion and have generally been in decline since 1997.
What the Morgentaler decision has meant for Canada is that abortion has settled into the domain in which it rightly belongs -- the health-care system. It is a medical procedure that, as two decades have proved, can be appropriately regulated by provincial Colleges of Physicians and Surgeons.
Canada's abortion statistics bear this out, including those related to the most controversial aspect of our no-law status -- that there are no legal restrictions on late-term abortions.
Procedures occurring after 20 weeks gestation make up less than 0.4 percent of abortions. Late-term abortion is rare, difficult to access and provided only in cases of serious maternal or fetal health problems.
It is inflammatory to suggest as does a recent national billboard campaign by LifeCanada that women do or can access abortion on demand when they are nine months pregnant.
To further demonstrate how abortion laws have no real power to impact actual abortion rates, consider a study by the Guttmacher Institute and the World Health Organization published in October 2007 by the journal Lancet.
It found that abortion rates in countries worldwide are similar regardless of whether the procedure is legal or not. "The legal status of abortion has never dissuaded women and couples, who, for whatever reason, seek to end pregnancy," said Beth Fredrick of the International Women's Health Coalition commenting on the study.
Herein lies another fundamental truth about abortion. That whether legal or not, safe or not, abortion is a choice often made by normal women all around the world. We cannot deny this. We could do worse as a society than to normalize abortion as a fact of human experience. Not normal as in blase, but normal as in standard, natural, common.
Canada, it could be argued, has been doing just this for the past 20 years. We have, to a lesser or greater degree, depending on where you live in this expansive country, normalized abortion as a medically necessary, reasonably accessible and compassionately delivered health-care procedure.
Canada also continues striving, through sexual health education and services, to reduce the need for abortion.
Perhaps this normalization is what most aggravates those who want to keep the abortion controversy simmering -- or boiling over onto the political stovetop.
Barbara Kay, also writing in the National Post last week, argued that Canadians who believe abortion should be restricted in some cases have been silenced. She noted astutely that "the 20-year anniversary of any transformative social decision is a good moment for a dispassionate review of the decision's consequences."
Could it be the consequences that have kept our politicians from responding to calls for discussion on legal restrictions to abortion?
After all, a dispassionate review reveals that abortion in Canada is being appropriately regulated by the medical profession with reasonable outcomes equal to or better than countries that do have laws restricting abortion.
All things considered, it appears the decision made 20 years ago today by the Supreme Court of Canada was wise, just and worthy of Canadians.
Laura Wershler is a sexual health advocate, writer and speaker. She is the executive director of Sexual Health Access Alberta
Tuesday, January 29, 2008
The Aftermath of Pro-Choice Demonstrations in Madrid, Barcelona and other Spanish Cities
Madrid, January 24, 2008.- The Spanish Federation of Family Planning (FPFE) and its member associations have supported the pro choice demonstrations which took place in Madrid and Barcelona yesterday at 7pm in Puerta del Sol and Plaça Sant Jaume respectively. The demonstrations demanded the depenalization of abortion and that abortions should be performed in and covered by the public health system, which is decentralized in Spain –which means that each autonomous community (the first-level political division of Spain) is responsible for its own self-management concerning Health.
Around 5,000 people participated in Madrid and 1,000 people in Barcelona. Additionally, other demonstrations took place in other eleven Spaniard cities such as Vigo, A Coruña, and Las Palmas de Gran Canaria,
In Madrid, more than 50 feminists and women’s organizations leaded the demonstration supported also by unions and political parties, to defend women’s right to choose with mottos such as “women give birth, women decide” and “against the persecution on women”.
In Barcelona, 30 organizations supported the demonstration as part of the campaign for the right to choose, under the motto “I have aborted, too”.
In cities of the Galicia Autonomous Community, such as Vigo and A Coruña, more than 300 people demanded that abortions should be performed in and covered by the public health system and expressed their solidarity with the health professionals in the abortion centres. Among other Galician organizations, the Marcha Mundial de las Mujeres (World March of Women) leads the campaign.
Every city is promoting a self-incrimination campaign that will be submitted to the Court next March, 8th.
In Las Palmas de Gran Canaria, feminist associations, sexual and reproductive health organizations and unions from the Autonomous Community of Canarias, led the demonstration to demand, among other things, that the Canarian Public Health System should perform and cover abortions.
The demonstrators in Madrid demanded the cease of the “violent campaign” against abortion which leaded by different conservative groups. In addition, the demonstrators have demanded further commitment from the Spanish Government to change the Law on Abortion (that was passed in 1985) -and definitely deleting from it the Penal Code- in order to protect women and medical professionals from the gaps of the current Law of Abortion.
In Madrid, more than 2,000 statements of self-incrimination both by women and men will be submitted to the Court that is judging the denounces presented in Madrid by the ultraconservative group “La vida importa” (Life matters).
Additionally, members of the Socialist Party (PSOE) participated in the demonstration in Madrid. They had to hear the claims from the demonstrators, who demanded the PSOE to fulfil the socialist’s promise to change the Law on Abortion included in the PSOE 2004 electoral program for the general elections, a failed promise now that the Zapatero Administration (2004-2008) is about to end.
THE DEBATE ON ABORTION.
Following 30 years of actions, reflections and mobilizations to support women’s right to abortion, Spain have finished 2007 and have begun 2008 with the fundamentalist conservatives attacking both women rights and abortive clinics in Madrid and Barcelona.
The FPFE understands that people working abortion clinics are being considered and treated as criminals. But the real scandal is that, even when the usual way to send judicial citations is via post mail, the Judges in Madrid and Barcelona have ordered the Civil Guard (a special police corps) to give personally and in their houses the citations to declare to the women that appear in the Clinics files.
This systematic campaign against abortion gathers the ultraconservative sectors of the Catholic Church and the extreme Right political movement. These groups have intimidated health professionals and women in the Clinics in Barcelona and Madrid and had presented denounces about the activities in the clinics that conduced to the arrests of professionals of the clinics.
The FPFE is for the protection of women rights, including the right to abortion.
“I have aborted, too” is one of the mottos chosen by the different organizations supporting yesterday’s demonstration in order to show solidarity with all women who have aborted and now feel fear and insecurity.
Yesterday, women and social organizations in Barcelona and Madrid and other Spanish cities had the opportunity to demonstrate their own support to change, among other things, the current legislation on abortion while reinforcing their right to decide on their own lives.
All in all, “I have aborted, too” is a motto in favour of justice. Additionally, contraception and the right to contraception is a right for women.
Once more, in the aftermath of both demonstrations, the FPFE demands:
The removal of abortion from the Spanish Penal Code.
The change of the current Law of Abortion to include the women’s right to decide upon their own bodies.
The normalization of abortion in the Spanish Public Health System (SPHS), guaranteeing the practice of abortion despite the fact of the conscientious objection which sometimes takes place among several doctors of the SPHS staff.
The support of the State of Rule guaranteeing women rights, including the right to abortion and the right of medical professionals to practice the medical profession linked to abortion, without intimidations or defamations and without affecting the right to abortion.
The guarantee of the Sexual and Reproductive Rights (SRR) for women which has already been acknowledged by Spain at the International Conference of Population and Development (ICPD, El Cairo, 1994) and the IV World Conference of Women (Beijing, 1995), i.e., giving women the right to get information on SRR, contraception and access to contraception.
Around 5,000 people participated in Madrid and 1,000 people in Barcelona. Additionally, other demonstrations took place in other eleven Spaniard cities such as Vigo, A Coruña, and Las Palmas de Gran Canaria,
In Madrid, more than 50 feminists and women’s organizations leaded the demonstration supported also by unions and political parties, to defend women’s right to choose with mottos such as “women give birth, women decide” and “against the persecution on women”.
In Barcelona, 30 organizations supported the demonstration as part of the campaign for the right to choose, under the motto “I have aborted, too”.
In cities of the Galicia Autonomous Community, such as Vigo and A Coruña, more than 300 people demanded that abortions should be performed in and covered by the public health system and expressed their solidarity with the health professionals in the abortion centres. Among other Galician organizations, the Marcha Mundial de las Mujeres (World March of Women) leads the campaign.
Every city is promoting a self-incrimination campaign that will be submitted to the Court next March, 8th.
In Las Palmas de Gran Canaria, feminist associations, sexual and reproductive health organizations and unions from the Autonomous Community of Canarias, led the demonstration to demand, among other things, that the Canarian Public Health System should perform and cover abortions.
The demonstrators in Madrid demanded the cease of the “violent campaign” against abortion which leaded by different conservative groups. In addition, the demonstrators have demanded further commitment from the Spanish Government to change the Law on Abortion (that was passed in 1985) -and definitely deleting from it the Penal Code- in order to protect women and medical professionals from the gaps of the current Law of Abortion.
In Madrid, more than 2,000 statements of self-incrimination both by women and men will be submitted to the Court that is judging the denounces presented in Madrid by the ultraconservative group “La vida importa” (Life matters).
Additionally, members of the Socialist Party (PSOE) participated in the demonstration in Madrid. They had to hear the claims from the demonstrators, who demanded the PSOE to fulfil the socialist’s promise to change the Law on Abortion included in the PSOE 2004 electoral program for the general elections, a failed promise now that the Zapatero Administration (2004-2008) is about to end.
THE DEBATE ON ABORTION.
Following 30 years of actions, reflections and mobilizations to support women’s right to abortion, Spain have finished 2007 and have begun 2008 with the fundamentalist conservatives attacking both women rights and abortive clinics in Madrid and Barcelona.
The FPFE understands that people working abortion clinics are being considered and treated as criminals. But the real scandal is that, even when the usual way to send judicial citations is via post mail, the Judges in Madrid and Barcelona have ordered the Civil Guard (a special police corps) to give personally and in their houses the citations to declare to the women that appear in the Clinics files.
This systematic campaign against abortion gathers the ultraconservative sectors of the Catholic Church and the extreme Right political movement. These groups have intimidated health professionals and women in the Clinics in Barcelona and Madrid and had presented denounces about the activities in the clinics that conduced to the arrests of professionals of the clinics.
The FPFE is for the protection of women rights, including the right to abortion.
“I have aborted, too” is one of the mottos chosen by the different organizations supporting yesterday’s demonstration in order to show solidarity with all women who have aborted and now feel fear and insecurity.
Yesterday, women and social organizations in Barcelona and Madrid and other Spanish cities had the opportunity to demonstrate their own support to change, among other things, the current legislation on abortion while reinforcing their right to decide on their own lives.
All in all, “I have aborted, too” is a motto in favour of justice. Additionally, contraception and the right to contraception is a right for women.
Once more, in the aftermath of both demonstrations, the FPFE demands:
The removal of abortion from the Spanish Penal Code.
The change of the current Law of Abortion to include the women’s right to decide upon their own bodies.
The normalization of abortion in the Spanish Public Health System (SPHS), guaranteeing the practice of abortion despite the fact of the conscientious objection which sometimes takes place among several doctors of the SPHS staff.
The support of the State of Rule guaranteeing women rights, including the right to abortion and the right of medical professionals to practice the medical profession linked to abortion, without intimidations or defamations and without affecting the right to abortion.
The guarantee of the Sexual and Reproductive Rights (SRR) for women which has already been acknowledged by Spain at the International Conference of Population and Development (ICPD, El Cairo, 1994) and the IV World Conference of Women (Beijing, 1995), i.e., giving women the right to get information on SRR, contraception and access to contraception.
Letter to the Editor- Irish Independent
Majority left out in abortion row James Burkill
The debate on the issue of abortion is dominated by extremists on both sides.
On one side of the coin, we have the absolutist 'pro-life' movement who believe that abortion is wrong, no matter what the circumstances.
On the other side of the coin, we have the 'pro-choice' absolutists who think that women should have a right to chose to abort.
Both sides argue from emotion and both sides are responsible for consistently reducing this important debate to a pointless mud-slinging match.
The losers in this are the reasonable majority who don't fit the mould of either of these simplistic positions.
We don't even have a name for those of us who don't believe that abortion should be off limits entirely and also don't believe that women should have the right to choose.
Those of us who believe that abortion should be allowed only under a specific, well-defined set of circumstances, as far as I can tell, are not even represented, and yet a poll in September suggests that we are in the majority.
Our position is more complicated than that of the pro-choice and pro-life lobbies and thus, we need to be well- informed.
You see, when you don't take an absolutist position, you can't determine exactly how you believe abortion should be legislated for without first hearing from experts in fields such as medicine, law and ethics. Unfortunately, we rarely hear from such experts in relation to the topic, thanks to the ignoramuses who hog the podium during any such debate.
I'm not suggesting that the issue can be settled by or decided by these experts. When it comes to issues of ethics and morality, it's up to each individual to make a decision on where they stand, but to make a decision, we need information and reasoned debate. If we can't get that with the pro-life and pro-choice campaigners around, maybe it's time we handed them their hats.
JAMES BURKILL,MAYNOOTH, CO KILDARE
The debate on the issue of abortion is dominated by extremists on both sides.
On one side of the coin, we have the absolutist 'pro-life' movement who believe that abortion is wrong, no matter what the circumstances.
On the other side of the coin, we have the 'pro-choice' absolutists who think that women should have a right to chose to abort.
Both sides argue from emotion and both sides are responsible for consistently reducing this important debate to a pointless mud-slinging match.
The losers in this are the reasonable majority who don't fit the mould of either of these simplistic positions.
We don't even have a name for those of us who don't believe that abortion should be off limits entirely and also don't believe that women should have the right to choose.
Those of us who believe that abortion should be allowed only under a specific, well-defined set of circumstances, as far as I can tell, are not even represented, and yet a poll in September suggests that we are in the majority.
Our position is more complicated than that of the pro-choice and pro-life lobbies and thus, we need to be well- informed.
You see, when you don't take an absolutist position, you can't determine exactly how you believe abortion should be legislated for without first hearing from experts in fields such as medicine, law and ethics. Unfortunately, we rarely hear from such experts in relation to the topic, thanks to the ignoramuses who hog the podium during any such debate.
I'm not suggesting that the issue can be settled by or decided by these experts. When it comes to issues of ethics and morality, it's up to each individual to make a decision on where they stand, but to make a decision, we need information and reasoned debate. If we can't get that with the pro-life and pro-choice campaigners around, maybe it's time we handed them their hats.
JAMES BURKILL,MAYNOOTH, CO KILDARE
Letters in the Irish Examiner - Monday January 28th
Irish Examiner Letters Page Monday January 28th
‘Abortion is murder’ – an absurd theory Seferin James
RORY O’DONOVAN (Letters, January 8) is mistaken to think Louise Caffrey (Letters, December 29) has failed to recognise the ideological grounds for opposition to the pro-choice position.
I assure Mr O’Donovan that everyone is well aware of the inescapably misogynist nature of the religious institutions that put the “firm belief” into his anti-choice position.
The ideological grounds in question are the grounds of the Catholic school he attended, the grounds of the church which he frequents, the grounds of Golgotha from which he derives the principle of noble suffering which he has effectively prescribed to women in crisis pregnancy. His insistence on using the term “murder” to describe abortion is a disingenuous but all too common equivocation between the two terms.
It is not only politically incorrect, a point to which Mr O’Donovan himself admits — it is also logically incorrect, a point to which “firm belief” is oblivious.
This equivocation reduces the former to absurdity and grossly mischaracterises the latter. Human life does not begin at conception — cell division begins at conception. That which is only potentially a person cannot itself be a person in actuality.
One cannot say that abortion is murder without reducing to absurdity what it means to be a human — the insubstantial notion that humanity just pops into existence when the soul supposedly enters into the foetus at the moment of conception. From where, we might well ask?
I argue that the meaning of moral values are ultimately derived from our ability to empathise with others.
In the case of abortion we are only capable of meaningfully empathising with the woman who finds herself pregnant without her reproductive consent.
To suggest otherwise is a theological fiction.
Seferin James
14 Cedar Square
Stillorgan
Co Dublin
Dutch figures are not understated Anne- Marie rey
I WISH to respond to the letter from Eilís Grealy headlined ‘Dutch abortion figures understated’ (January 21).
This is one of those endlessly ruminated anti-abortion myths. In fact, Dutch abortion figures are not understated, but among the most accurate worldwide.
Every abortion is notified, including the so-called overtime treatments (very early abortions up to 44 days from last menstrual period).
One simple reason for the accuracy of the figures is that doctors only get paid by social insurance for those abortions they notify. You can be sure that Dutch doctors do not like very much to do unpaid work — no more than doctors in other countries.
The Dutch abortion rate per 1,000 women aged 15-44 (which is a more telling measure for the occurrence of abortions than the abortion ratio per 100 births) has remained stable since 2001, after a short period of rising slightly in the 1990s. It was 8.6/1,000 in 2006.
Switzerland has followed the Dutch model and after a very liberal abortion practice for many years, it legalised abortion on request in the first 12 weeks of pregnancy in 2002.
In 2006 — the forth year under the new law — the abortion rate continued to fall and reached an all-time low, with 6/1,000 women, a rate even lower than the Dutch one.
These rates are among the lowest worldwide (note that there are no more illegal abortions in these two countries).
The reasons are good sex education and ready availability of contraception — the morning-after pill, for example, is available over the counter.
Anne-Marie Rey
Abortion-information
Grabenstr. 21
3052 Zollikofen
Bern
Switzerland
IN his letter on abortion (January 8), Rory O’Donovan seeks to draw a distinction between pro-choice campaigners and care for the life of the unborn.
It is a gross injustice to women to suggest the decision to terminate a pregnancy signals a lack of care for the unborn.
Since Mr O’Donovan has never carried a child, one cannot expect him to understand the experience, but to suggest that a woman is not acutely aware of the potential life inside her, of the future prospects of that life and of the world of experience it will be born into — that is just preposterous.
Mr O’Donovan’s suggestion that people who seek a legal choice in the matter have “more in common with those who show concern over the carbon emissions resulting from a trip abroad than the implications for the life of an unborn child” is, I suspect, made in a somewhat sarcastic spirit — but it is in fact very relevant.
Concern over global warming is all to do with the future and those who come after us. While anti-choice campaigners have a deep concern for the life of the unborn child, the reality is that beyond attempting to secure the child’s future, they are powerless over the circumstances into which he or she will be born — and they show little concern about that.
The fact is that women already have the “veto over the lives of their unborn children”, which Mr O’Donovan is so against.
It is a responsibility conferred by virtue of their physical make-up and by modern medical science, and a number of Irish women each day choose to exercise that responsibility by ending their pregnancy, often with no guidance whatsoever.
If the anti-choice lobby was less concerned with salving its own conscience and more with the lives of the mother and and her unborn child, surely it would advocate legislation that includes mandatory counselling for women in crisis situations so they can be sure the decision they make takes into account all the ethics?
Nicki ffrench Davis Georges Quay Cork
‘Abortion is murder’ – an absurd theory Seferin James
RORY O’DONOVAN (Letters, January 8) is mistaken to think Louise Caffrey (Letters, December 29) has failed to recognise the ideological grounds for opposition to the pro-choice position.
I assure Mr O’Donovan that everyone is well aware of the inescapably misogynist nature of the religious institutions that put the “firm belief” into his anti-choice position.
The ideological grounds in question are the grounds of the Catholic school he attended, the grounds of the church which he frequents, the grounds of Golgotha from which he derives the principle of noble suffering which he has effectively prescribed to women in crisis pregnancy. His insistence on using the term “murder” to describe abortion is a disingenuous but all too common equivocation between the two terms.
It is not only politically incorrect, a point to which Mr O’Donovan himself admits — it is also logically incorrect, a point to which “firm belief” is oblivious.
This equivocation reduces the former to absurdity and grossly mischaracterises the latter. Human life does not begin at conception — cell division begins at conception. That which is only potentially a person cannot itself be a person in actuality.
One cannot say that abortion is murder without reducing to absurdity what it means to be a human — the insubstantial notion that humanity just pops into existence when the soul supposedly enters into the foetus at the moment of conception. From where, we might well ask?
I argue that the meaning of moral values are ultimately derived from our ability to empathise with others.
In the case of abortion we are only capable of meaningfully empathising with the woman who finds herself pregnant without her reproductive consent.
To suggest otherwise is a theological fiction.
Seferin James
14 Cedar Square
Stillorgan
Co Dublin
Dutch figures are not understated Anne- Marie rey
I WISH to respond to the letter from Eilís Grealy headlined ‘Dutch abortion figures understated’ (January 21).
This is one of those endlessly ruminated anti-abortion myths. In fact, Dutch abortion figures are not understated, but among the most accurate worldwide.
Every abortion is notified, including the so-called overtime treatments (very early abortions up to 44 days from last menstrual period).
One simple reason for the accuracy of the figures is that doctors only get paid by social insurance for those abortions they notify. You can be sure that Dutch doctors do not like very much to do unpaid work — no more than doctors in other countries.
The Dutch abortion rate per 1,000 women aged 15-44 (which is a more telling measure for the occurrence of abortions than the abortion ratio per 100 births) has remained stable since 2001, after a short period of rising slightly in the 1990s. It was 8.6/1,000 in 2006.
Switzerland has followed the Dutch model and after a very liberal abortion practice for many years, it legalised abortion on request in the first 12 weeks of pregnancy in 2002.
In 2006 — the forth year under the new law — the abortion rate continued to fall and reached an all-time low, with 6/1,000 women, a rate even lower than the Dutch one.
These rates are among the lowest worldwide (note that there are no more illegal abortions in these two countries).
The reasons are good sex education and ready availability of contraception — the morning-after pill, for example, is available over the counter.
Anne-Marie Rey
Abortion-information
Grabenstr. 21
3052 Zollikofen
Bern
Switzerland
IN his letter on abortion (January 8), Rory O’Donovan seeks to draw a distinction between pro-choice campaigners and care for the life of the unborn.
It is a gross injustice to women to suggest the decision to terminate a pregnancy signals a lack of care for the unborn.
Since Mr O’Donovan has never carried a child, one cannot expect him to understand the experience, but to suggest that a woman is not acutely aware of the potential life inside her, of the future prospects of that life and of the world of experience it will be born into — that is just preposterous.
Mr O’Donovan’s suggestion that people who seek a legal choice in the matter have “more in common with those who show concern over the carbon emissions resulting from a trip abroad than the implications for the life of an unborn child” is, I suspect, made in a somewhat sarcastic spirit — but it is in fact very relevant.
Concern over global warming is all to do with the future and those who come after us. While anti-choice campaigners have a deep concern for the life of the unborn child, the reality is that beyond attempting to secure the child’s future, they are powerless over the circumstances into which he or she will be born — and they show little concern about that.
The fact is that women already have the “veto over the lives of their unborn children”, which Mr O’Donovan is so against.
It is a responsibility conferred by virtue of their physical make-up and by modern medical science, and a number of Irish women each day choose to exercise that responsibility by ending their pregnancy, often with no guidance whatsoever.
If the anti-choice lobby was less concerned with salving its own conscience and more with the lives of the mother and and her unborn child, surely it would advocate legislation that includes mandatory counselling for women in crisis situations so they can be sure the decision they make takes into account all the ethics?
Nicki ffrench Davis Georges Quay Cork
Wednesday, January 23, 2008
As Abortion Rate Drops, Use of RU-486 Is On Rise
As Abortion Rate Drops, Use of RU-486 Is on Rise
by Rob Stein The Washington Post
Thirty-five years after the Supreme Court's landmark Roe v. Wade decision, a pill that has largely faded from the rancorous public debate over abortion has slowly and quietly begun to transform the experience of ending a pregnancy in the United States.
The French abortion pill RU-486, on the market since 2000, has become an increasingly common alternative, making abortion less clinical and more private. At a time when the overall number of abortions has been steadily declining, RU-486-induced abortions have been rising by 22 percent a year and now account for 14 percent of the total -- and more than one in five early abortions performed by the ninth week of pregnancy.
The pill, often called "miffy" after its chemical name mifepristone and brand name Mifeprex, also has helped slow the decline in abortion providers, as more physicians who previously did not perform the procedure discreetly start to prescribe the pill.
"The impact and the promise is huge," said Beth Jordan, medical director of the Association of Reproductive Health Professionals. "It's going a long way towards normalizing abortion."
When the Food and Drug Administration approved mifepristone in 2000, some predicted it would revolutionize the abortion experience and debate by enabling women to get an abortion from any doctor, neutralizing one of opponents' most potent strategies -- picketing abortion clinics.
"The thinking initially was that this was going to change everything. There was a lot of hype. That didn't pan out," said Carole Joffe, a professor of sociology at the University of California at Davis. "But the impact has been happening gradually as it slowly and steadily is becoming integrated into the medical system."
Judi Gilbert, 41, a nurse in Philadelphia, opted for mifepristone in 2005 when she had her second abortion. She had a 3-year-old son and was about to start a new job.
"It was something I could do at home and be with my husband," Gilbert said of taking the pill. "It was a decision we made together alone, and we were able to take care of it this way alone. It was just a much more private affair."
She added: "I wouldn't say it was easy -- it's never easy to terminate a pregnancy. But in the grand scheme of things, it was much more pleasant than a surgical procedure."
Gilbert is one of more than 840,000 U.S. women who have used mifepristone since it was approved, according to Danco Laboratories, which sells it.
The drug ends a pregnancy by blocking the hormone progesterone. Women take the pill in the doctor's office and then go home, where they take another drug, misoprostol, to trigger contractions, essentially causing a miscarriage. Women then return to the doctor within about two weeks to make sure the process worked.
The price of the procedure varies. Standard abortions typically cost about $400, and the pill can cost the same to about $100 more.
About 150,000 of the 1.2 million abortions in the United States in 2006 were done with medication, the Guttmacher Institute, a nonprofit reproductive-health research organization, estimated recently.
More than half of abortion providers now offer the option, a 70 percent increase from the first half of 2001, Guttmacher said.
"Mifepristone is clearly starting to become an important part of the abortion provision in the United States," said Lawrence Finer, who studies the drug at Guttmacher. "I think we'll continue to see increases."
He noted that in some European countries, more than 60 percent of abortions are performed with the drug.
The increase is alarming to abortion opponents, who are expecting thousands to gather in the District today to protest Roe v. Wade on its 35th anniversary.
"This troubles me," said Randall K. O'Bannon of the National Right to Life Committee. "It obviously shows that the marketing efforts have been effective in getting doctors to introduce this into their practices."
O'Bannon questioned the drug's safety, citing a handful of reports of women who have died from severe complications from bacterial infections. "The idea that doctors are beginning to offer something that has a record of causing some serious problems is very troubling," he said. Supporters say that it remains unclear whether the complications were related to the drug and that overall the method has been shown to be extremely safe.
"The availability of mifepristone gives women another safe and effective way to terminate a pregnancy," said Vicki Saporta, president of the National Abortion Federation, which estimates that 83 percent of its 400 member clinics offer the drug.
The increase in mifepristone use has been fueled in part by more doctors and clinics that previously did not perform abortions now offering the drug. Guttmacher identified at least 119 and said those practices have slowed the decline in abortion services. The number of providers fell 2 percent from 1994 to 2005 -- a much slower decline than before the drug became available. Without mifepristone, the drop would have been 8 percent.
Ruth Lesnewski, a family physician in New York, did not perform abortions until mifepristone was approved.
"It allows abortion to happen in a more private, secure setting -- a doctor's office and a woman's home, rather than an easily targeted clinic," she said. "It's been a surprisingly smooth and rewarding experience for such a fraught area of life. My patients really tremendously appreciate being able to end an unwanted pregnancy privately and quickly."
Other doctors have begun to offer mifepristone in addition to surgical abortion.
"For some women, they like to have a more active role rather than just having something done to them," said Deborah Oyer, a family-practice doctor in Seattle. "For some, it feels in some ways more natural because it feels more like their body is doing it."
Some doctors walk a delicate line. One doctor in Albuquerque, for example, said she does not use in the pill at one of her offices but does offer it along with standard abortions at a clinic where she works At another clinic, she provides only the pill.
"My office is in a politically charged part of the community, so I try to be as diplomatic as possible," she said, speaking on the condition of anonymity. "But at my other office, we can do an abortion where no one has to know -- not even the support staff."
The proportion of abortions being done with the drug varies widely, with some providers saying mifepristone accounts for about 10 percent and others reporting it accounts for two-thirds.
"We see 10 to 12 patients a week who want it," said Mary Frank, who runs the Memphis Center for Reproductive Health. "I've noticed that the women who want this have really done their homework. They know exactly what the process is and really have made a very conscious decision about their choice."
Women's experiences also vary widely.
"Some women say, 'It's the most horrible thing that ever happened and I'll never do it again,' and some women say, 'Heck, my period was worse than that,' " said Catherine McKegney, a family physician in St. Paul, Minn.
Mary, 25, an office administrator in Seattle, opted for mifepristone in December when she became pregnant and decided with her fiance that they were not ready to become parents.
"I liked the idea of being more in control," said Mary, who asked that her full name not be used. "I had some really, really bad cramps and had to take some Vicodin and ibuprofen to calm them down. But other than the cramps, it was pretty painless."
Victoria Reyes, 24, used mifepristone in 2006 when she became pregnant just before she was about to graduate from Ohio State University.
"It was one of the most difficult decisions I ever made in my life," she said. "My boyfriend and I got together and decided we were not in any position to financially afford a child. I chose it because it seemed like a more natural way."
But Reyes was surprised by how physically traumatic it turned out to be.
"It was one of the most painful experiences I've ever had," she said. "Not only were the cramps really bad, I was sweating and had a headache. I threw up at one point. It was pretty bad."
Reyes also had to take a second dose when an ultrasound showed she had not completed the abortion, requiring her to return to the clinic for a second time to confirm that the process was complete.
"I think I'm still glad I picked it," Reyes said. "I just wanted to be home and keep it private."
by Rob Stein The Washington Post
Thirty-five years after the Supreme Court's landmark Roe v. Wade decision, a pill that has largely faded from the rancorous public debate over abortion has slowly and quietly begun to transform the experience of ending a pregnancy in the United States.
The French abortion pill RU-486, on the market since 2000, has become an increasingly common alternative, making abortion less clinical and more private. At a time when the overall number of abortions has been steadily declining, RU-486-induced abortions have been rising by 22 percent a year and now account for 14 percent of the total -- and more than one in five early abortions performed by the ninth week of pregnancy.
The pill, often called "miffy" after its chemical name mifepristone and brand name Mifeprex, also has helped slow the decline in abortion providers, as more physicians who previously did not perform the procedure discreetly start to prescribe the pill.
"The impact and the promise is huge," said Beth Jordan, medical director of the Association of Reproductive Health Professionals. "It's going a long way towards normalizing abortion."
When the Food and Drug Administration approved mifepristone in 2000, some predicted it would revolutionize the abortion experience and debate by enabling women to get an abortion from any doctor, neutralizing one of opponents' most potent strategies -- picketing abortion clinics.
"The thinking initially was that this was going to change everything. There was a lot of hype. That didn't pan out," said Carole Joffe, a professor of sociology at the University of California at Davis. "But the impact has been happening gradually as it slowly and steadily is becoming integrated into the medical system."
Judi Gilbert, 41, a nurse in Philadelphia, opted for mifepristone in 2005 when she had her second abortion. She had a 3-year-old son and was about to start a new job.
"It was something I could do at home and be with my husband," Gilbert said of taking the pill. "It was a decision we made together alone, and we were able to take care of it this way alone. It was just a much more private affair."
She added: "I wouldn't say it was easy -- it's never easy to terminate a pregnancy. But in the grand scheme of things, it was much more pleasant than a surgical procedure."
Gilbert is one of more than 840,000 U.S. women who have used mifepristone since it was approved, according to Danco Laboratories, which sells it.
The drug ends a pregnancy by blocking the hormone progesterone. Women take the pill in the doctor's office and then go home, where they take another drug, misoprostol, to trigger contractions, essentially causing a miscarriage. Women then return to the doctor within about two weeks to make sure the process worked.
The price of the procedure varies. Standard abortions typically cost about $400, and the pill can cost the same to about $100 more.
About 150,000 of the 1.2 million abortions in the United States in 2006 were done with medication, the Guttmacher Institute, a nonprofit reproductive-health research organization, estimated recently.
More than half of abortion providers now offer the option, a 70 percent increase from the first half of 2001, Guttmacher said.
"Mifepristone is clearly starting to become an important part of the abortion provision in the United States," said Lawrence Finer, who studies the drug at Guttmacher. "I think we'll continue to see increases."
He noted that in some European countries, more than 60 percent of abortions are performed with the drug.
The increase is alarming to abortion opponents, who are expecting thousands to gather in the District today to protest Roe v. Wade on its 35th anniversary.
"This troubles me," said Randall K. O'Bannon of the National Right to Life Committee. "It obviously shows that the marketing efforts have been effective in getting doctors to introduce this into their practices."
O'Bannon questioned the drug's safety, citing a handful of reports of women who have died from severe complications from bacterial infections. "The idea that doctors are beginning to offer something that has a record of causing some serious problems is very troubling," he said. Supporters say that it remains unclear whether the complications were related to the drug and that overall the method has been shown to be extremely safe.
"The availability of mifepristone gives women another safe and effective way to terminate a pregnancy," said Vicki Saporta, president of the National Abortion Federation, which estimates that 83 percent of its 400 member clinics offer the drug.
The increase in mifepristone use has been fueled in part by more doctors and clinics that previously did not perform abortions now offering the drug. Guttmacher identified at least 119 and said those practices have slowed the decline in abortion services. The number of providers fell 2 percent from 1994 to 2005 -- a much slower decline than before the drug became available. Without mifepristone, the drop would have been 8 percent.
Ruth Lesnewski, a family physician in New York, did not perform abortions until mifepristone was approved.
"It allows abortion to happen in a more private, secure setting -- a doctor's office and a woman's home, rather than an easily targeted clinic," she said. "It's been a surprisingly smooth and rewarding experience for such a fraught area of life. My patients really tremendously appreciate being able to end an unwanted pregnancy privately and quickly."
Other doctors have begun to offer mifepristone in addition to surgical abortion.
"For some women, they like to have a more active role rather than just having something done to them," said Deborah Oyer, a family-practice doctor in Seattle. "For some, it feels in some ways more natural because it feels more like their body is doing it."
Some doctors walk a delicate line. One doctor in Albuquerque, for example, said she does not use in the pill at one of her offices but does offer it along with standard abortions at a clinic where she works At another clinic, she provides only the pill.
"My office is in a politically charged part of the community, so I try to be as diplomatic as possible," she said, speaking on the condition of anonymity. "But at my other office, we can do an abortion where no one has to know -- not even the support staff."
The proportion of abortions being done with the drug varies widely, with some providers saying mifepristone accounts for about 10 percent and others reporting it accounts for two-thirds.
"We see 10 to 12 patients a week who want it," said Mary Frank, who runs the Memphis Center for Reproductive Health. "I've noticed that the women who want this have really done their homework. They know exactly what the process is and really have made a very conscious decision about their choice."
Women's experiences also vary widely.
"Some women say, 'It's the most horrible thing that ever happened and I'll never do it again,' and some women say, 'Heck, my period was worse than that,' " said Catherine McKegney, a family physician in St. Paul, Minn.
Mary, 25, an office administrator in Seattle, opted for mifepristone in December when she became pregnant and decided with her fiance that they were not ready to become parents.
"I liked the idea of being more in control," said Mary, who asked that her full name not be used. "I had some really, really bad cramps and had to take some Vicodin and ibuprofen to calm them down. But other than the cramps, it was pretty painless."
Victoria Reyes, 24, used mifepristone in 2006 when she became pregnant just before she was about to graduate from Ohio State University.
"It was one of the most difficult decisions I ever made in my life," she said. "My boyfriend and I got together and decided we were not in any position to financially afford a child. I chose it because it seemed like a more natural way."
But Reyes was surprised by how physically traumatic it turned out to be.
"It was one of the most painful experiences I've ever had," she said. "Not only were the cramps really bad, I was sweating and had a headache. I threw up at one point. It was pretty bad."
Reyes also had to take a second dose when an ultrasound showed she had not completed the abortion, requiring her to return to the clinic for a second time to confirm that the process was complete.
"I think I'm still glad I picked it," Reyes said. "I just wanted to be home and keep it private."
Monday, January 21, 2008
Bolivia's 'Bad Births' Sit on Political Sidelines
Bolivia's 'Bad Births' Sit on Political Sidelines
By Jean Friedman-Rudovsky - WeNews correspondent
LA PAZ, Bolivia (WOMENSENEWS)--Bolivia's 255-delegate Constituent Assembly under President Evo Morales--the country's first indigenous leader and widely considered one of the region's most leftist heads of state--last month narrowly avoided adding a ban on all abortion to its new constitution, regardless of the dangers to a woman's life.
Surprise? Not in Latin America.
While abortion rights may be a rough dividing line between left and right in the United States, progressive party rule here is no ticket to pro-choice advancement in this region.
In the past two years, Nicaragua's government of former revolutionary Sandinistas has banned all abortions. The president of Uruguay--leader of his country's historic left-wing party--has vowed to veto parliamentary attempts to legalize abortion. And Venezuelans' push to decriminalize the procedure has come to a virtual halt under socialist President Hugo Chavez.
Here in Bolivia the recent abortion controversy revolved around five words--"from the moment of conception"--which were to follow the text's guarantee to the right to life.
The phrase would have effectively outlawed all abortion in Bolivia, a major change for the country. The country is drafting a new constitution to give Bolivia's historically marginalized poor and indigenous majority a chance to help create a new foundational text.
Technically, abortion here was legalized in 1973 for victims of sexual assault or to prevent a life-threatening pregnancy. In practice, however, abortions are often performed without any legal inspection and the country has never seen an abortion provider prosecuted.
Bolivia has one of the highest abortion rates in the world: up to 80,000 procedures annually in a country of only 9 million people, according to the United Nations.
Prohibitive Expense
Many are relatively safe procedures performed in more than a dozen clinics around the country. But the average $150 fee is prohibitive for most in South America's poorest nation, so many look for alternative methods.
"First, I tried vaginal inserts," says one Bolivian woman, referring to a widely available ulcer drug that has become a popular do-it-yourself abortion option because of the medicine's side effects. "When that didn't work I found someone to do it for $30. I passed out during it and when I woke up, I was bloody and he was gone."
She was relatively lucky; at least one woman a day here ends up dead in this type of swallow-hard-and-take-the-risk medical care.
Despite the high number of deaths, talking about abortion remains taboo here in Bolivia.
Catholicism, the constitutionally established official religion, helps explain that. In Catholic schools, children are required to watch a video of a womb undergoing an abortion. It was church authorities who brought the conception clause to Constituent Assembly delegates when the body first began its proceedings.
Anti-abortion sentiment is widespread in secular life as well, says Claudia Lopez, a 31-year-old pro-choicer in Cochabamba. "Regardless of religion, we learn that conception isn't an option, it's our function," she says. "Women who abort live with a lifetime of guilt."
Entrenched Resistance
Major newspapers run pictures of a thumb-size fetus in a glass jar alongside articles about abortion. Staff in medical clinics often try to dissuade their patients from having abortions, telling them it is better to choose life than murder, say interviewees.
Meanwhile leftist indigenous women--who have been key players in Bolivia's recent political battles--have, for the most part, steered clear of the issue.
Paul Bustillos, political director for La Paz-based Catholics for the Right to Choose, says that's because pro-choice leaders have not engaged the country's indigenous majority.
"Here, the women's movement is known as a middle- or upper-class, white and often foreigner-led phenomenon," says Bustillos.
An indication of this disconnect: Many abortions are performed in rural areas where indigenous people predominate, yet the procedures are not referred to by their clinical name. Instead of "abortions" they are called "bad births" and are followed by cleansing rituals.
Balky Assembly
In the end, Morales' ruling Movement Towards Socialism party blocked the conception clause from the final text of the constitution, which still must be approved by national vote later this year. But it was like pulling teeth, say sources in the assembly, where about 1 in 4 delegates is female.
Bustillos says Catholics for the Right to Choose went into a "state of emergency" when the conception clause was introduced. Staff and volunteers distributed educational materials, led workshops and implored delegates not to doom their daughters and granddaughters to unwanted or risky pregnancies.
A key point, Bustillos says, was telling delegates that Bolivia's new constitution should enhance existing rights and not take them away.
Pro-choice advocates here know that in Latin America, a region that counts over 4 million abortions each year and up to 10,000 resulting deaths, Bolivia's resistance is not likely to dissolve any time soon.
"It's not that they don't understand, because inevitably they've all had a loved one go through this," says a Bolivian woman who recently had an abortion, referring to the region's new political leadership. "It's about the strong societal force pushing against acceptability. And overcoming that is going to take more than a few years of left-wing governments."
Jean Friedman-Rudovsky is the correspondent for Time magazine in Bolivia and is a founding editor of Ukhampacha Bolivia, www.ubnoticias.org/es, a bilingual online journal on Bolivian and Latin American politics.
Women's eNews welcomes your comments. E-mail us at editors@womensenews.org .
For more information:
Catholics for a Right to Choose (in Spanish): - http://www.catolicasporelderechoadecidir.org/inicio.php
International Planned Parenthood Federation, Western Hemisphere: - http://www.ippfwhr.org/site/c.kuLRJ5MTKvH/b.2506867/k.BF43/Home.htm
Center for Reproductive Rights, Shadow Report on Bolivia (PDF format) - [Adobe PDF format]: - http://www.reproductiverights.org/pdf/sr_bol_0401_eng.pdf
Note: Women's eNews is not responsible for the content of external Internet sites and the contents of Web pages we link to may change without notice.
By Jean Friedman-Rudovsky - WeNews correspondent
LA PAZ, Bolivia (WOMENSENEWS)--Bolivia's 255-delegate Constituent Assembly under President Evo Morales--the country's first indigenous leader and widely considered one of the region's most leftist heads of state--last month narrowly avoided adding a ban on all abortion to its new constitution, regardless of the dangers to a woman's life.
Surprise? Not in Latin America.
While abortion rights may be a rough dividing line between left and right in the United States, progressive party rule here is no ticket to pro-choice advancement in this region.
In the past two years, Nicaragua's government of former revolutionary Sandinistas has banned all abortions. The president of Uruguay--leader of his country's historic left-wing party--has vowed to veto parliamentary attempts to legalize abortion. And Venezuelans' push to decriminalize the procedure has come to a virtual halt under socialist President Hugo Chavez.
Here in Bolivia the recent abortion controversy revolved around five words--"from the moment of conception"--which were to follow the text's guarantee to the right to life.
The phrase would have effectively outlawed all abortion in Bolivia, a major change for the country. The country is drafting a new constitution to give Bolivia's historically marginalized poor and indigenous majority a chance to help create a new foundational text.
Technically, abortion here was legalized in 1973 for victims of sexual assault or to prevent a life-threatening pregnancy. In practice, however, abortions are often performed without any legal inspection and the country has never seen an abortion provider prosecuted.
Bolivia has one of the highest abortion rates in the world: up to 80,000 procedures annually in a country of only 9 million people, according to the United Nations.
Prohibitive Expense
Many are relatively safe procedures performed in more than a dozen clinics around the country. But the average $150 fee is prohibitive for most in South America's poorest nation, so many look for alternative methods.
"First, I tried vaginal inserts," says one Bolivian woman, referring to a widely available ulcer drug that has become a popular do-it-yourself abortion option because of the medicine's side effects. "When that didn't work I found someone to do it for $30. I passed out during it and when I woke up, I was bloody and he was gone."
She was relatively lucky; at least one woman a day here ends up dead in this type of swallow-hard-and-take-the-risk medical care.
Despite the high number of deaths, talking about abortion remains taboo here in Bolivia.
Catholicism, the constitutionally established official religion, helps explain that. In Catholic schools, children are required to watch a video of a womb undergoing an abortion. It was church authorities who brought the conception clause to Constituent Assembly delegates when the body first began its proceedings.
Anti-abortion sentiment is widespread in secular life as well, says Claudia Lopez, a 31-year-old pro-choicer in Cochabamba. "Regardless of religion, we learn that conception isn't an option, it's our function," she says. "Women who abort live with a lifetime of guilt."
Entrenched Resistance
Major newspapers run pictures of a thumb-size fetus in a glass jar alongside articles about abortion. Staff in medical clinics often try to dissuade their patients from having abortions, telling them it is better to choose life than murder, say interviewees.
Meanwhile leftist indigenous women--who have been key players in Bolivia's recent political battles--have, for the most part, steered clear of the issue.
Paul Bustillos, political director for La Paz-based Catholics for the Right to Choose, says that's because pro-choice leaders have not engaged the country's indigenous majority.
"Here, the women's movement is known as a middle- or upper-class, white and often foreigner-led phenomenon," says Bustillos.
An indication of this disconnect: Many abortions are performed in rural areas where indigenous people predominate, yet the procedures are not referred to by their clinical name. Instead of "abortions" they are called "bad births" and are followed by cleansing rituals.
Balky Assembly
In the end, Morales' ruling Movement Towards Socialism party blocked the conception clause from the final text of the constitution, which still must be approved by national vote later this year. But it was like pulling teeth, say sources in the assembly, where about 1 in 4 delegates is female.
Bustillos says Catholics for the Right to Choose went into a "state of emergency" when the conception clause was introduced. Staff and volunteers distributed educational materials, led workshops and implored delegates not to doom their daughters and granddaughters to unwanted or risky pregnancies.
A key point, Bustillos says, was telling delegates that Bolivia's new constitution should enhance existing rights and not take them away.
Pro-choice advocates here know that in Latin America, a region that counts over 4 million abortions each year and up to 10,000 resulting deaths, Bolivia's resistance is not likely to dissolve any time soon.
"It's not that they don't understand, because inevitably they've all had a loved one go through this," says a Bolivian woman who recently had an abortion, referring to the region's new political leadership. "It's about the strong societal force pushing against acceptability. And overcoming that is going to take more than a few years of left-wing governments."
Jean Friedman-Rudovsky is the correspondent for Time magazine in Bolivia and is a founding editor of Ukhampacha Bolivia, www.ubnoticias.org/es, a bilingual online journal on Bolivian and Latin American politics.
Women's eNews welcomes your comments. E-mail us at editors@womensenews.org .
For more information:
Catholics for a Right to Choose (in Spanish): - http://www.catolicasporelderechoadecidir.org/inicio.php
International Planned Parenthood Federation, Western Hemisphere: - http://www.ippfwhr.org/site/c.kuLRJ5MTKvH/b.2506867/k.BF43/Home.htm
Center for Reproductive Rights, Shadow Report on Bolivia (PDF format) - [Adobe PDF format]: - http://www.reproductiverights.org/pdf/sr_bol_0401_eng.pdf
Note: Women's eNews is not responsible for the content of external Internet sites and the contents of Web pages we link to may change without notice.
Friday, January 18, 2008
300 at UK Parliament Rally to Defend a Woman’s Right to Choose
300 pro-choice supporters packed into Parliament last night to launch
campaigning to defend a Woman’s Right to Choose. The launch, on Wednesday 16
January organised by Abortion Rights, saw a new generation of women unite
with those from previous campaigns that have defeated anti-abortion attacks
– all affirming their determination to defend a woman’s right to choose this
time round too. The crowds were so big an overflow room was also filled.
The threat to current law hinges around anti-abortion attempts to use the
Human Fertilisation and Embryology Bill to attack the current time limit and
grounds for legal abortion.
Speakers from the Lords and Commons and from all three main parties, from
the TUC, women’s, disability rights and student movements urged supporters
to begin lobbying parliamentarians now and warned that the well funded
abortion opponents are already active.
The meeting heard from Baroness Joyce Gould, Chair of the All Party
Parliamentary Pro-Choice and Sexual Health Group, who outlined the Bill’s
current progress in the Lords where the first vote on abortion is expected
on Monday 21st January.
Baroness Jenny Tonge Vice-Chair of the All Party Parliamentary Pro-Choice
and Sexual Health Group urged people confused about the issues to ‘put
themselves in the shoes of a woman who is pregnant and doesn’t want to be
-only then can you really begin to understand the importance of the right to
choose for women.’.
Diane Abbott MP argued that contrary to the anti-abortionists own rhetoric,
their position wasn’t pro-women or pro-family. Anti-abortionists were
fundamentally ‘anti-woman’ she said, to huge applause. Their goals were in
essence “about controlling women and their sexuality”, about “rolling back
every advance women have made over the last thirty years” and taking the
view of women that “if they’re going to have sex they should suffer for it”.
Emily Thornberry MP criticised anti-abortion proposals for a ‘cooling off’
period before women can have an abortion saying it was “condescending to
suggest women can’t be trusted to make such a fundamental decision about
their lives”.
Wendy Savage, Doctors for a Woman’s Choice on Abortion, and a renowned
advocate of women’s right to choose defended current rights to abortion up
to 24 weeks arguing that “the women most affected by a change in the time
limit are the youngest and most vulnerable and we’ve got to resist that”.
Alex Kemp NUS Disabled Students Officer said “restricting access to
abortion, for whatever reason, does not further the rights of disabled
women”. “Disabled students condemn the emotive and unnecessary association
between disability and abortion. Women have the right to choose to do with
their bodies what they like - disabled people do not wish to interfere with
that right.”
Numerous speakers also supported Abortion Rights’ position that far from
restricting rights, 40 years after the Abortion Act, current unfair barriers
to accessing abortion should be ended. Specifically that doctors’ effective
right of veto of over women’s abortion decision should be ended and that
abortion should be allowed in more settings and by trained nurses to end
delays.
Abortion Rights announced that a mass lobby of parliament, further rallies,
protests and demonstrations would be called in the coming weeks and months
to coincide with key stages of the Bill’s progress in the Commons.
A protest on 6th February in London against anti-abortion MP Anne
Widdecome’s road show promoting anti-abortion goals around the Bill was
announced (subject to police permission).
Notes
Abortion Rights is the national pro-choice campaign. It is supported by the
TUC, many of the national trade unions, the National Union of Students and
hundreds of individual members. It works closely with the All Party
Parliamentary Pro-Choice and Sexual Health Group and the Voice for Choice
coalition of pro-choice organisations. www.abortionrights.org.uk
Speakers at the event were Baroness Joyce Gould; Baroness Jenny Tonge; Emily
Thornberry MP; John Bercow MP; Katy Clark MP; Diane Abbott MP; Laura Moffatt
MP; Evan Harris MP; Narmada Thiranagama TUC women’s equality policy officer;
Wendy Savage, Doctors for A Woman's Choice on Abortion; Anni Marjoram,
adviser to the Mayor of London; Alex Kemp, NUS Disabled Students' Campaign;
Anne Quesney, Abortion Rights; Marge Berer, Voice for Choice; Katherine
Rake, Fawcett Society;
campaigning to defend a Woman’s Right to Choose. The launch, on Wednesday 16
January organised by Abortion Rights, saw a new generation of women unite
with those from previous campaigns that have defeated anti-abortion attacks
– all affirming their determination to defend a woman’s right to choose this
time round too. The crowds were so big an overflow room was also filled.
The threat to current law hinges around anti-abortion attempts to use the
Human Fertilisation and Embryology Bill to attack the current time limit and
grounds for legal abortion.
Speakers from the Lords and Commons and from all three main parties, from
the TUC, women’s, disability rights and student movements urged supporters
to begin lobbying parliamentarians now and warned that the well funded
abortion opponents are already active.
The meeting heard from Baroness Joyce Gould, Chair of the All Party
Parliamentary Pro-Choice and Sexual Health Group, who outlined the Bill’s
current progress in the Lords where the first vote on abortion is expected
on Monday 21st January.
Baroness Jenny Tonge Vice-Chair of the All Party Parliamentary Pro-Choice
and Sexual Health Group urged people confused about the issues to ‘put
themselves in the shoes of a woman who is pregnant and doesn’t want to be
-only then can you really begin to understand the importance of the right to
choose for women.’.
Diane Abbott MP argued that contrary to the anti-abortionists own rhetoric,
their position wasn’t pro-women or pro-family. Anti-abortionists were
fundamentally ‘anti-woman’ she said, to huge applause. Their goals were in
essence “about controlling women and their sexuality”, about “rolling back
every advance women have made over the last thirty years” and taking the
view of women that “if they’re going to have sex they should suffer for it”.
Emily Thornberry MP criticised anti-abortion proposals for a ‘cooling off’
period before women can have an abortion saying it was “condescending to
suggest women can’t be trusted to make such a fundamental decision about
their lives”.
Wendy Savage, Doctors for a Woman’s Choice on Abortion, and a renowned
advocate of women’s right to choose defended current rights to abortion up
to 24 weeks arguing that “the women most affected by a change in the time
limit are the youngest and most vulnerable and we’ve got to resist that”.
Alex Kemp NUS Disabled Students Officer said “restricting access to
abortion, for whatever reason, does not further the rights of disabled
women”. “Disabled students condemn the emotive and unnecessary association
between disability and abortion. Women have the right to choose to do with
their bodies what they like - disabled people do not wish to interfere with
that right.”
Numerous speakers also supported Abortion Rights’ position that far from
restricting rights, 40 years after the Abortion Act, current unfair barriers
to accessing abortion should be ended. Specifically that doctors’ effective
right of veto of over women’s abortion decision should be ended and that
abortion should be allowed in more settings and by trained nurses to end
delays.
Abortion Rights announced that a mass lobby of parliament, further rallies,
protests and demonstrations would be called in the coming weeks and months
to coincide with key stages of the Bill’s progress in the Commons.
A protest on 6th February in London against anti-abortion MP Anne
Widdecome’s road show promoting anti-abortion goals around the Bill was
announced (subject to police permission).
Notes
Abortion Rights is the national pro-choice campaign. It is supported by the
TUC, many of the national trade unions, the National Union of Students and
hundreds of individual members. It works closely with the All Party
Parliamentary Pro-Choice and Sexual Health Group and the Voice for Choice
coalition of pro-choice organisations. www.abortionrights.org.uk
Speakers at the event were Baroness Joyce Gould; Baroness Jenny Tonge; Emily
Thornberry MP; John Bercow MP; Katy Clark MP; Diane Abbott MP; Laura Moffatt
MP; Evan Harris MP; Narmada Thiranagama TUC women’s equality policy officer;
Wendy Savage, Doctors for A Woman's Choice on Abortion; Anni Marjoram,
adviser to the Mayor of London; Alex Kemp, NUS Disabled Students' Campaign;
Anne Quesney, Abortion Rights; Marge Berer, Voice for Choice; Katherine
Rake, Fawcett Society;
South African Abortion Bill Votes Counted
Abortion bill votes counted
The controversial Choice on Termination of Pregnancy Amendment Bill was passed by the National Assembly on Thursday by 266 votes to 52, with 12 abstentions.
The African Christian Democratic Party, Freedom Front, Federation of Democrats and Inkatha Freedom Party all voted against the measure, while the Democratic Alliance allowed its members a free vote on the matter.
The so-called abortion bill seeks, among other things, to amend existing legislation to allow certain public and private clinics to perform abortions without first obtaining government approval.
According to an attached memorandum, the bill empowers provincial health MECs to approve facilities at which abortions may be carried out.
'Do not let the blood of more innocent babied be on your hands'
"[Among the bill's objects is to] allow all public and private facilities that have a 24-hour maternity service to terminate pregnancies of up to and including 12 weeks without seeking approval from the Member of the Executive Council concerned."
Speaking during a declaration of vote, the ACDP's Cheryllyn Dudley said her party opposed the bill in the strongest possible terms.
"We call on members of this House to do the same. Do not let the blood of more innocent babied be on your hands," she implored.
Research showed nine out of 10 South Africans believed abortion was "morally wrong", Dudley said.
The DA's Mike Waters said his party has allowed members a free vote on the bill.
The bill 'gave women the right to choose'
The DA had two concerns with the measure, including that counselling for those seeking an abortion should be mandatory, and not non-mandatory as specified in the bill.
Further, doctors, midwives and nurses should have the right to conscientiously object to performing an abortion, and this right should be written into the law.
African National Congress MP James Ngculu told the House the bill gave women the right to choose.
The bill will now be sent to the National Council of Provinces for concurrence.
Earlier on Thursday, pro-life groups had urged MPs to reject the measure, saying they should not pass the bill in its current form.
"A major point highlighted in all pro-life submissions included that women must receive adequate counselling in which all the risks (both physical and psychological) are explained in the counselling session prior to the abortion," Taryn Hodgson, spokeswoman of the Christian Action Network said in a statement. - Sapa
Published on the Web by IOL on 2008-01-17 16:46:51
The controversial Choice on Termination of Pregnancy Amendment Bill was passed by the National Assembly on Thursday by 266 votes to 52, with 12 abstentions.
The African Christian Democratic Party, Freedom Front, Federation of Democrats and Inkatha Freedom Party all voted against the measure, while the Democratic Alliance allowed its members a free vote on the matter.
The so-called abortion bill seeks, among other things, to amend existing legislation to allow certain public and private clinics to perform abortions without first obtaining government approval.
According to an attached memorandum, the bill empowers provincial health MECs to approve facilities at which abortions may be carried out.
'Do not let the blood of more innocent babied be on your hands'
"[Among the bill's objects is to] allow all public and private facilities that have a 24-hour maternity service to terminate pregnancies of up to and including 12 weeks without seeking approval from the Member of the Executive Council concerned."
Speaking during a declaration of vote, the ACDP's Cheryllyn Dudley said her party opposed the bill in the strongest possible terms.
"We call on members of this House to do the same. Do not let the blood of more innocent babied be on your hands," she implored.
Research showed nine out of 10 South Africans believed abortion was "morally wrong", Dudley said.
The DA's Mike Waters said his party has allowed members a free vote on the bill.
The bill 'gave women the right to choose'
The DA had two concerns with the measure, including that counselling for those seeking an abortion should be mandatory, and not non-mandatory as specified in the bill.
Further, doctors, midwives and nurses should have the right to conscientiously object to performing an abortion, and this right should be written into the law.
African National Congress MP James Ngculu told the House the bill gave women the right to choose.
The bill will now be sent to the National Council of Provinces for concurrence.
Earlier on Thursday, pro-life groups had urged MPs to reject the measure, saying they should not pass the bill in its current form.
"A major point highlighted in all pro-life submissions included that women must receive adequate counselling in which all the risks (both physical and psychological) are explained in the counselling session prior to the abortion," Taryn Hodgson, spokeswoman of the Christian Action Network said in a statement. - Sapa
Published on the Web by IOL on 2008-01-17 16:46:51
Thursday, January 17, 2008
Long Roe to Hoe- From the Nation by Frances Kissling and Kate Michelman
From The Nation by Frances Kissling and Kate Michelman
Long Roe to Hoe
It’s been thirty-five years since the Supreme Court put the jewel in the crown of reproductive rights and civil liberties in America by affirming in Roe v. Wade a woman’s constitutional right to choose abortion. Immediately, the government authorized the use of Medicaid funds for poor women who choose abortion and the United States became a world leader in supporting reproductive health services.
Opposition to abortion, however, rapidly became the galvanizing issue in the emerging culture wars. Right-wing leaders from Senator Paul Laxalt to Paul Weyrich seized on abortion as a wedge issue to engage fundamentalist Christians in supporting the full agenda of the then–new right. Women are still paying the price for the success of this campaign. While Roe was not overturned, it was systematically eviscerated, and long-accepted reproductive health services such as birth control became controversial. These days the United States has one of the most punitive and regressive policies on reproductive health in the developed world. To reverse this turn to the far right, women’s health advocates must seek not only to protect abortion rights but to restore the whole range of reproductive health services, pushing for this broader agenda to be at the center of any progressive platform.
Looking at Europe, we can see how things would be different if reproductive health policy attended to women’s needs rather than the demands of a fundamentalist Christian right. Almost without exception, in Western European countries where abortions are legal, they are included in national healthcare plans. They do not require parental consent or notice for adolescents seeking abortion; contraceptives are reasonably priced, covered by health insurance and often available without prescription; teens and adults have access to emergency contraception in hospitals or over the counter at pharmacies; and abstinence-only sex education is rare.
When European women choose to have babies, they generally get free prenatal care and excellent midwifery services and birthing options. They receive paid medical and family leave. Those who are unemployed, disabled or ill are not penalized for having children but receive adequate resources to care for their family. Single mothers who work have access to professional daycare.
And the countries with these policies have lower unintended pregnancy rates and thus lower abortion rates.
The major European development agencies do not seek to control social values in the countries that receive their aid, nor do they deny funding to agencies or countries where abstinence is not put forward as the only option for preventing either pregnancy or disease. Family-planning funds are not withheld if local agencies provide access to or support safe and legal abortion.
While prochoice and antiabortion groups in the United States have argued about the minutiae of abortion practice, women’s economic security and reproductive health have been severely undermined by far-reaching changes in public policy. Given this broad assault on women, it is no longer ethically sound or politically wise to see abortion as the centerpiece of women’s struggle for freedom and equality. In the “change” election of 2008, it is critical that all candidates who claim to be prochoice define choice more broadly. They must make a commitment to fully restoring reproductive health and dignity to all American women regardless of their economic status. Likewise, a commitment should be made to a foreign policy that supports these services and rights for women in the developing world.
The sorry state of US reproductive health policy also requires serious shifts within the women’s and the abortion-rights movements, where we were privileged to serve as leaders for many years. So-called inside-the-Beltway strategies need to adopt a comprehensive progressive agenda that makes abortion rights and access part of the pursuit of justice for working and low-income women. Should the 2008 election result in a Democratic President and Congress, advocates need to insist on much more than we asked of the Clinton Administration. “Change” needs to go beyond the expansion of unpaid family and medical leave and the provision of emergency contraception to women who have been raped. Certain bottom-line commitments must be made not only by presidential candidates but by Congressional ones. These include commitments to paid family and medical leave; revocation of those aspects of welfare reform that penalize women with children and those who become pregnant while on public assistance; nationwide inclusion of abortion, family planning and emergency contraception for women in all national healthcare plans; and comprehensive, high-quality sex education and confidential reproductive healthcare for adolescents.
Having learned the hard way that Supreme Court decisions can fail us, we need to frame our case in the court of public opinion, and listen more attentively and respond more fully to the public’s concern about men’s as well as women’s responsibilities to prevent unwanted pregnancies and to parent wisely and lovingly. Roe v. Wade was a socially transforming decision that in many ways was ahead of its time. For women much of the task of social transformation is still before us. And it will be achieved only when we truly engage the public on the many issues that will ensure women’s equality and security.
Frances Kissling and Kate Michelman
Frances Kissling and Kate Michelman were longtime presidents of, respectively, Catholics for a Free Choice and NARAL Pro-choice America. Michelman is the author of Protecting the Right to Choose.
Long Roe to Hoe
It’s been thirty-five years since the Supreme Court put the jewel in the crown of reproductive rights and civil liberties in America by affirming in Roe v. Wade a woman’s constitutional right to choose abortion. Immediately, the government authorized the use of Medicaid funds for poor women who choose abortion and the United States became a world leader in supporting reproductive health services.
Opposition to abortion, however, rapidly became the galvanizing issue in the emerging culture wars. Right-wing leaders from Senator Paul Laxalt to Paul Weyrich seized on abortion as a wedge issue to engage fundamentalist Christians in supporting the full agenda of the then–new right. Women are still paying the price for the success of this campaign. While Roe was not overturned, it was systematically eviscerated, and long-accepted reproductive health services such as birth control became controversial. These days the United States has one of the most punitive and regressive policies on reproductive health in the developed world. To reverse this turn to the far right, women’s health advocates must seek not only to protect abortion rights but to restore the whole range of reproductive health services, pushing for this broader agenda to be at the center of any progressive platform.
Looking at Europe, we can see how things would be different if reproductive health policy attended to women’s needs rather than the demands of a fundamentalist Christian right. Almost without exception, in Western European countries where abortions are legal, they are included in national healthcare plans. They do not require parental consent or notice for adolescents seeking abortion; contraceptives are reasonably priced, covered by health insurance and often available without prescription; teens and adults have access to emergency contraception in hospitals or over the counter at pharmacies; and abstinence-only sex education is rare.
When European women choose to have babies, they generally get free prenatal care and excellent midwifery services and birthing options. They receive paid medical and family leave. Those who are unemployed, disabled or ill are not penalized for having children but receive adequate resources to care for their family. Single mothers who work have access to professional daycare.
And the countries with these policies have lower unintended pregnancy rates and thus lower abortion rates.
The major European development agencies do not seek to control social values in the countries that receive their aid, nor do they deny funding to agencies or countries where abstinence is not put forward as the only option for preventing either pregnancy or disease. Family-planning funds are not withheld if local agencies provide access to or support safe and legal abortion.
While prochoice and antiabortion groups in the United States have argued about the minutiae of abortion practice, women’s economic security and reproductive health have been severely undermined by far-reaching changes in public policy. Given this broad assault on women, it is no longer ethically sound or politically wise to see abortion as the centerpiece of women’s struggle for freedom and equality. In the “change” election of 2008, it is critical that all candidates who claim to be prochoice define choice more broadly. They must make a commitment to fully restoring reproductive health and dignity to all American women regardless of their economic status. Likewise, a commitment should be made to a foreign policy that supports these services and rights for women in the developing world.
The sorry state of US reproductive health policy also requires serious shifts within the women’s and the abortion-rights movements, where we were privileged to serve as leaders for many years. So-called inside-the-Beltway strategies need to adopt a comprehensive progressive agenda that makes abortion rights and access part of the pursuit of justice for working and low-income women. Should the 2008 election result in a Democratic President and Congress, advocates need to insist on much more than we asked of the Clinton Administration. “Change” needs to go beyond the expansion of unpaid family and medical leave and the provision of emergency contraception to women who have been raped. Certain bottom-line commitments must be made not only by presidential candidates but by Congressional ones. These include commitments to paid family and medical leave; revocation of those aspects of welfare reform that penalize women with children and those who become pregnant while on public assistance; nationwide inclusion of abortion, family planning and emergency contraception for women in all national healthcare plans; and comprehensive, high-quality sex education and confidential reproductive healthcare for adolescents.
Having learned the hard way that Supreme Court decisions can fail us, we need to frame our case in the court of public opinion, and listen more attentively and respond more fully to the public’s concern about men’s as well as women’s responsibilities to prevent unwanted pregnancies and to parent wisely and lovingly. Roe v. Wade was a socially transforming decision that in many ways was ahead of its time. For women much of the task of social transformation is still before us. And it will be achieved only when we truly engage the public on the many issues that will ensure women’s equality and security.
Frances Kissling and Kate Michelman
Frances Kissling and Kate Michelman were longtime presidents of, respectively, Catholics for a Free Choice and NARAL Pro-choice America. Michelman is the author of Protecting the Right to Choose.
Abortions Down 25% From Peak- Los Angeles Times
Abortions down 25% from peak
But a study says more women are choosing medication, rather than surgery, to end pregnancies.
By Stephanie Simon
Los Angeles Times Staff Writer
January 17, 2008
A comprehensive study of abortion in America underscores a striking change in the landscape, with ever-fewer pregnant women choosing abortion and those who do increasingly opting to avoid surgical clinics.
The number of abortions has plunged to 1.2 million a year, down 25% since peaking in 1990, according to a report released today -- days before the 35th anniversary of Roe vs. Wade, the Supreme Court ruling that legalized abortion.
In the early 1980s, nearly 1 in 3 pregnant women chose abortion. The most recent data show that proportion is closer to 1 in 5.
"That's a significant drop, and it's encouraging," said Randall K. O'Bannon, director of education and research for the antiabortion group National Right to Life.
Women looking to end early pregnancies are gravitating to medication abortions, in which they take two pills under a doctor's supervision to induce miscarriage. This approach lets them avoid surgery -- and the protesters who often picket clinics -- and expel the embryo in the privacy of their homes. The Food and Drug Administration approved the pills in 2000 for use through the seventh week of pregnancy.
By 2005, the most recent year covered by the report, the pills accounted for 13% of all abortions.
The research was conducted by the Guttmacher Institute, a New York-based nonprofit that focuses on reproductive issues. The institute supports abortion rights and has received funding in the past from Planned Parenthood. Abortion opponents, however, generally view its statistics as reliable.
The Guttmacher report came to no conclusions about why the abortion landscape had changed. But that didn't stop activists on both sides from speculating -- and using the data to press their political agendas.
Abortion rights advocates suggested women may be avoiding unwanted pregnancies, thanks in part to the morning-after pill, emergency contraception that is sold without a prescription to women 18 and older.
Led by Planned Parenthood, activists have pledged to spend much of 2008 lobbying for laws to make all forms of birth control cheaper and more widely accessible. They also plan to push states to require sex-education classes that teach teens about contraception.
A political tactics manual recently developed for Planned Parenthood asserts that voters respond well to such issues -- especially when they're framed with buzzwords like "prevention," "protection" and "personal responsibility."
Dwell too much on abortion, and the broader liberal agenda will bog down, said Kathy Bonk, a consultant who developed the strategy. "It matters where you start the conversation," she said. "If you start on abortion, you don't get off abortion."
Conservatives, by contrast, are eager to keep the focus on abortion.
They contend that the more women learn about the procedure, the less likely they are to choose it. The rapid growth of crisis pregnancy centers -- which offer free diapers, parenting classes and other support -- has helped cut the number of abortions, they say. But just as important, in their view, are laws in more than 30 states mandating counseling before an abortion.
Some of the material given to women at such sessions is false or misleading -- for example, warnings that abortion raises the risk of breast cancer or causes post-traumatic stress disorder. Abortion rights supporters also object that many of the counseling brochures use photos of fetal development through nine months, though 90% of abortions take place in the first trimester.
Abortion opponents view such material as a vital tool to turn women against abortion; they plan to lobby to expand this type of counseling.
"We are making progress, state by state and law by law," said Denise M. Burke, vice president of Americans United for Life.
Some of the biggest drops in the abortion rate, however, have come in states that do not impose tight restrictions.
Oregon, for instance, was rated this week by Americans United for Life as the nation's "least pro-life state," yet its abortion rate dropped 25% from 2000 to 2005 -- more than any state except Wyoming.
California also was ranked hostile territory by Americans United for Life, but its abortion rate fell 13%, significantly more than the national average. "Abortion rate" refers to the number of abortions per 1,000 women of reproductive age.
The data suggest that the decline in abortions may be due not to legal restrictions, but to a shift in "socio-cultural mores" -- in other words, women's attitudes, said John Seery, a professor at Pomona College who studies the politics of abortion.
"Right-to-lifers should take heart that abortion rates have been dropping, despite the movement's failure to reverse Roe vs. Wade," he said. To build upon that, Seery added, the antiabortion movement should focus on continuing to "change hearts and minds."
In addition to the data on abortion rates, the Guttmacher report offered the first comprehensive census of abortion providers since 2000.
The number of abortion clinics nationwide was down 15%, a net loss of four dozen surgical clinics. But other women's health centers -- and doctors in private practice -- filled the gap by offering medical abortions.
That trend may have political implications.
Abortion clinics have been besieged by "an escalation of pickets and protests," said Cecile Richards, president of the Planned Parenthood Federation of America. It's much harder for protesters to identify a physician in private practice.
It also may be tougher for states to regulate medical abortions.
Missouri recently passed a law requiring doctors who dispense the abortion pill to turn their offices into full surgical suites. But a judge put the law on hold, pending a legal challenge.
"Increasing reliance on nonsurgical abortions is a problem for the antiabortion movement," said Alan I. Abramowitz, a political scientist at Emory University in Atlanta. "There is little popular support for restricting such abortions."
On the other hand, the trend isn't a clear victory for abortion rights advocates either. "It's harder for protesters to target these physicians, but it's also harder for women to find them," said Rachel K. Jones, a senior research associate at Guttmacher.
She said most doctors who prescribed the abortion pill worked in urban areas, so access to abortion had not improved for rural women.
More than 1 in 4 abortion patients reports traveling at least 50 miles to reach a provider. Nationwide, 87% of counties have no abortion services, a figure that has remained constant since 2000.
In compiling such statistics, Jones said she was struck by how difficult it was to persuade abortion doctors to share information about their practice because they feared reprisals from protesters.
"We used to be able to do this type of survey every year or every other year," she said. "Now, people are really reluctant to give you the information."
stephanie.simon@latimes.com
But a study says more women are choosing medication, rather than surgery, to end pregnancies.
By Stephanie Simon
Los Angeles Times Staff Writer
January 17, 2008
A comprehensive study of abortion in America underscores a striking change in the landscape, with ever-fewer pregnant women choosing abortion and those who do increasingly opting to avoid surgical clinics.
The number of abortions has plunged to 1.2 million a year, down 25% since peaking in 1990, according to a report released today -- days before the 35th anniversary of Roe vs. Wade, the Supreme Court ruling that legalized abortion.
In the early 1980s, nearly 1 in 3 pregnant women chose abortion. The most recent data show that proportion is closer to 1 in 5.
"That's a significant drop, and it's encouraging," said Randall K. O'Bannon, director of education and research for the antiabortion group National Right to Life.
Women looking to end early pregnancies are gravitating to medication abortions, in which they take two pills under a doctor's supervision to induce miscarriage. This approach lets them avoid surgery -- and the protesters who often picket clinics -- and expel the embryo in the privacy of their homes. The Food and Drug Administration approved the pills in 2000 for use through the seventh week of pregnancy.
By 2005, the most recent year covered by the report, the pills accounted for 13% of all abortions.
The research was conducted by the Guttmacher Institute, a New York-based nonprofit that focuses on reproductive issues. The institute supports abortion rights and has received funding in the past from Planned Parenthood. Abortion opponents, however, generally view its statistics as reliable.
The Guttmacher report came to no conclusions about why the abortion landscape had changed. But that didn't stop activists on both sides from speculating -- and using the data to press their political agendas.
Abortion rights advocates suggested women may be avoiding unwanted pregnancies, thanks in part to the morning-after pill, emergency contraception that is sold without a prescription to women 18 and older.
Led by Planned Parenthood, activists have pledged to spend much of 2008 lobbying for laws to make all forms of birth control cheaper and more widely accessible. They also plan to push states to require sex-education classes that teach teens about contraception.
A political tactics manual recently developed for Planned Parenthood asserts that voters respond well to such issues -- especially when they're framed with buzzwords like "prevention," "protection" and "personal responsibility."
Dwell too much on abortion, and the broader liberal agenda will bog down, said Kathy Bonk, a consultant who developed the strategy. "It matters where you start the conversation," she said. "If you start on abortion, you don't get off abortion."
Conservatives, by contrast, are eager to keep the focus on abortion.
They contend that the more women learn about the procedure, the less likely they are to choose it. The rapid growth of crisis pregnancy centers -- which offer free diapers, parenting classes and other support -- has helped cut the number of abortions, they say. But just as important, in their view, are laws in more than 30 states mandating counseling before an abortion.
Some of the material given to women at such sessions is false or misleading -- for example, warnings that abortion raises the risk of breast cancer or causes post-traumatic stress disorder. Abortion rights supporters also object that many of the counseling brochures use photos of fetal development through nine months, though 90% of abortions take place in the first trimester.
Abortion opponents view such material as a vital tool to turn women against abortion; they plan to lobby to expand this type of counseling.
"We are making progress, state by state and law by law," said Denise M. Burke, vice president of Americans United for Life.
Some of the biggest drops in the abortion rate, however, have come in states that do not impose tight restrictions.
Oregon, for instance, was rated this week by Americans United for Life as the nation's "least pro-life state," yet its abortion rate dropped 25% from 2000 to 2005 -- more than any state except Wyoming.
California also was ranked hostile territory by Americans United for Life, but its abortion rate fell 13%, significantly more than the national average. "Abortion rate" refers to the number of abortions per 1,000 women of reproductive age.
The data suggest that the decline in abortions may be due not to legal restrictions, but to a shift in "socio-cultural mores" -- in other words, women's attitudes, said John Seery, a professor at Pomona College who studies the politics of abortion.
"Right-to-lifers should take heart that abortion rates have been dropping, despite the movement's failure to reverse Roe vs. Wade," he said. To build upon that, Seery added, the antiabortion movement should focus on continuing to "change hearts and minds."
In addition to the data on abortion rates, the Guttmacher report offered the first comprehensive census of abortion providers since 2000.
The number of abortion clinics nationwide was down 15%, a net loss of four dozen surgical clinics. But other women's health centers -- and doctors in private practice -- filled the gap by offering medical abortions.
That trend may have political implications.
Abortion clinics have been besieged by "an escalation of pickets and protests," said Cecile Richards, president of the Planned Parenthood Federation of America. It's much harder for protesters to identify a physician in private practice.
It also may be tougher for states to regulate medical abortions.
Missouri recently passed a law requiring doctors who dispense the abortion pill to turn their offices into full surgical suites. But a judge put the law on hold, pending a legal challenge.
"Increasing reliance on nonsurgical abortions is a problem for the antiabortion movement," said Alan I. Abramowitz, a political scientist at Emory University in Atlanta. "There is little popular support for restricting such abortions."
On the other hand, the trend isn't a clear victory for abortion rights advocates either. "It's harder for protesters to target these physicians, but it's also harder for women to find them," said Rachel K. Jones, a senior research associate at Guttmacher.
She said most doctors who prescribed the abortion pill worked in urban areas, so access to abortion had not improved for rural women.
More than 1 in 4 abortion patients reports traveling at least 50 miles to reach a provider. Nationwide, 87% of counties have no abortion services, a figure that has remained constant since 2000.
In compiling such statistics, Jones said she was struck by how difficult it was to persuade abortion doctors to share information about their practice because they feared reprisals from protesters.
"We used to be able to do this type of survey every year or every other year," she said. "Now, people are really reluctant to give you the information."
stephanie.simon@latimes.com
US Abortion Rate Continues Long-Term Decline
U.S. ABORTION RATE CONTINUES LONG-TERM DECLINE,
FALLING TO LOWEST LEVEL SINCE 1974;
MORE EFFORT STILL NEEDED TO REDUCE UNINTENDED PREGNANCY
Increased Use of Medication Abortion Stems Decline in Providers
In 2005, the U.S. abortion rate declined to 19.4 abortions per 1,000 women aged 15–44, continuing the downward trend that started after the abortion rate peaked at 29.3 in 1981, according to a new Guttmacher Institute census of U.S. abortion providers. The abortion rate is now at its lowest level since 1974. The number of abortions declined as well, to a total of 1.2 million in 2005, 25% below the all-time high of 1.6 million abortions in 1990.
Despite these declines, slightly more than one in five pregnancies ended in abortion in 2005, an indicator of how much still needs to be done to help women and their partners avoid unintended pregnancy. “Our policymakers at the state and federal levels need to understand that behind virtually every abortion is an unintended pregnancy, so we must redouble our efforts towards prevention, through better access to contraception,” says Sharon L. Camp, president and CEO of the Guttmacher Institute.
Even as the long-term decline in the U.S. abortion rate continued, the new study also found that early medication abortion services expanded substantially between 2000 and 2005, as growing numbers of providers offered the service, including some that previously did not offer surgical abortion services. Fifty-seven percent of all known abortion providers now offer medication abortion services, compared with 33% in early 2001. Medication abortion accounted for 13% (161,000) of all abortions performed in 2005, and 22% of all eligible abortions (those performed prior to nine weeks’ gestation). According to recent government reports, abortions are occurring earlier, when the procedure is safer; increased access to medication abortion can help accelerate that trend.
“For a long time, nearly 90% of abortions in the U.S. have taken place in the first trimester, but in recent years, women having an abortion have been able to do so earlier and earlier in the first trimester. Currently, more than six in 10 abortions occur within the first eight weeks of pregnancy, and almost three in 10 take place at six weeks or earlier,” says Rachel Jones, lead researcher on the new survey. “Medication abortion, which provides women with an additional option early in pregnancy, clearly reinforces this very positive trend.”
The decline in the number of U.S. abortion providers, which had been substantial over the past decade, slowed dramatically between 2000 and 2005: The number of providers declined just 2% over this period, partly because of a surge in the number of providers that offer only medication abortion services. Without them, the number of providers would have declined by 8%. Overall, the number of providers declined in 26 states and the District of Columbia, increased in 15 states and remained stable in nine.
This analysis is based on the Guttmacher Institute’s 14th census of all known abortion providers in the United States. The study, “Abortion in the United States: Incidence and Access to Services, 2005,” will appear in the March 2008 issue of Perspectives on Sexual and Reproductive Health.
Additional materials can be found online:
• Facts on Induced Abortion in the United States – national overview fact sheet
• State Facts About Abortion – state-specific fact sheets
• An Overview of Abortion in the United States – slide show on the current state of abortion
• Trends in Abortion in the United States, 1973–2005 – slide show presenting trends since Roe
• Trends in Abortion by State – slide shows presenting trend data for all 50 states and the District of Columbia
from Guttmacher Institute newsletter.
The Guttmacher Institute—www.guttmacher.org—advances sexual and reproductive health worldwide through an interrelated program of social science research, policy analysis and public education.
Again, to view the full article please visit: http://www.guttmacher.org/pubs/journals/4000608.pdf
FALLING TO LOWEST LEVEL SINCE 1974;
MORE EFFORT STILL NEEDED TO REDUCE UNINTENDED PREGNANCY
Increased Use of Medication Abortion Stems Decline in Providers
In 2005, the U.S. abortion rate declined to 19.4 abortions per 1,000 women aged 15–44, continuing the downward trend that started after the abortion rate peaked at 29.3 in 1981, according to a new Guttmacher Institute census of U.S. abortion providers. The abortion rate is now at its lowest level since 1974. The number of abortions declined as well, to a total of 1.2 million in 2005, 25% below the all-time high of 1.6 million abortions in 1990.
Despite these declines, slightly more than one in five pregnancies ended in abortion in 2005, an indicator of how much still needs to be done to help women and their partners avoid unintended pregnancy. “Our policymakers at the state and federal levels need to understand that behind virtually every abortion is an unintended pregnancy, so we must redouble our efforts towards prevention, through better access to contraception,” says Sharon L. Camp, president and CEO of the Guttmacher Institute.
Even as the long-term decline in the U.S. abortion rate continued, the new study also found that early medication abortion services expanded substantially between 2000 and 2005, as growing numbers of providers offered the service, including some that previously did not offer surgical abortion services. Fifty-seven percent of all known abortion providers now offer medication abortion services, compared with 33% in early 2001. Medication abortion accounted for 13% (161,000) of all abortions performed in 2005, and 22% of all eligible abortions (those performed prior to nine weeks’ gestation). According to recent government reports, abortions are occurring earlier, when the procedure is safer; increased access to medication abortion can help accelerate that trend.
“For a long time, nearly 90% of abortions in the U.S. have taken place in the first trimester, but in recent years, women having an abortion have been able to do so earlier and earlier in the first trimester. Currently, more than six in 10 abortions occur within the first eight weeks of pregnancy, and almost three in 10 take place at six weeks or earlier,” says Rachel Jones, lead researcher on the new survey. “Medication abortion, which provides women with an additional option early in pregnancy, clearly reinforces this very positive trend.”
The decline in the number of U.S. abortion providers, which had been substantial over the past decade, slowed dramatically between 2000 and 2005: The number of providers declined just 2% over this period, partly because of a surge in the number of providers that offer only medication abortion services. Without them, the number of providers would have declined by 8%. Overall, the number of providers declined in 26 states and the District of Columbia, increased in 15 states and remained stable in nine.
This analysis is based on the Guttmacher Institute’s 14th census of all known abortion providers in the United States. The study, “Abortion in the United States: Incidence and Access to Services, 2005,” will appear in the March 2008 issue of Perspectives on Sexual and Reproductive Health.
Additional materials can be found online:
• Facts on Induced Abortion in the United States – national overview fact sheet
• State Facts About Abortion – state-specific fact sheets
• An Overview of Abortion in the United States – slide show on the current state of abortion
• Trends in Abortion in the United States, 1973–2005 – slide show presenting trends since Roe
• Trends in Abortion by State – slide shows presenting trend data for all 50 states and the District of Columbia
from Guttmacher Institute newsletter.
The Guttmacher Institute—www.guttmacher.org—advances sexual and reproductive health worldwide through an interrelated program of social science research, policy analysis and public education.
Again, to view the full article please visit: http://www.guttmacher.org/pubs/journals/4000608.pdf
Reproductive Rights Alliance in South Africa welcomes adoption of the Choice on Termination of Pregnancy Amendment Act
17 January 2008
PRESS RELEASE:
Reproductive Rights Alliance welcomes adoption of the Choice on Termination of Pregnancy Amendment Act
Today parliament passed the Choice on Termination of Pregnancy Amendment Act. This comes after a process of public hearings undertaken by both houses of parliament. The extended consultation processes came as a result of a Constitutional Court ruling. However, the substance of the law was not in question. In brief, the law is aimed at expediting the designation of facilities; extending the pool of service providers; and clamping down on unscrupulous practitioners.
It builds on the principal Act, the Choice on Termination of Pregnancy Act no 92 of 1996, which has resulted in a positive impact on women's health. In particular it:
. Raised awareness of choices available to pregnant women, enabling
them to discuss options available to them and to access services.
. Significantly reduced the number of women dying by 91% as a result
of backstreet abortions. Also reduced health complications by 50%.
. Reduced public health care costs of treating complications resulting
from backstreet abortion; and
. Provided greater access to services, especially to poor, young and
rural women.
Parliamentary hearings in 2002 identified barriers that prevented optimal access. This resulted in the 2004 Amendment Act that increases and expands access to safe and legal pregnancy terminations, especially for poor and rural women. It does so in the following ways:
. Decentralisation to provinces helps the government improve the
quality of reproductive health services to women, especially at local level.
. It increases the pool of health care providers and the quality of
services.
. It improves provincial administration of reproductive health
services, by enabling better internal accountability (eg. planning, record-keeping, monitoring services etc).
. It prevents the proliferation of illegal abortion clinics and
providers and strengthens the arm of the state in prosecuting these.
Little or no opposition to these provisions was expressed in the public consultation process. The opposition that was voiced was directed at provisions of the principal act (such as conscientious objection) and was aimed at limiting access to services and eroding women's constitutional right to reproductive choices and health-care. Such opposition is well-resourced and is part of a wider, global campaign to attack and erode these rights. It is characterised by strategies that include:
. Repeated and unsuccessful legal challenges to the principal Act;
. Appealing to emotion and the use of graphic materials to stigmatise
termination providers and services, as well as the women who use them;
. The spread of misinformation, including the use of pseudo-science
that draws spurious links between terminations and women's ill health
. Creating a climate of confusion and guilt that intimidates health
workers and clients
For example, the right of health workers to conscientious objection is often raised as a problem. There is no evidence that this requires a legislative response. Despite claims to the contrary, no one has laid a complaint with either Democratic Nursing Organisation of South Africa (DENOSA) or South African Medical Association (SAMA) about being forced to perform TOPs.
The Constitution makes provision for conscientious objection, but also mandates access to reproductive health care and requires non-discrimination.
This provides a framework for genuine issues of conscientious objection to be addressed at management level. However, competency in pregnancy termination care is necessary for all health workers. The Health Professions Council of South Africa (HPCSA) requires doctors to be generalists, able to provide termination of pregnancy for women in various states of life.
Calls for conscientious objection do the following:
. Promote discrimination against patients based on the kind of service
they require
. Disrupt the patient - health worker relationship by prioritising the
rights of the provider over those of the patient
. Marginalise termination services, placing them outside of the core
reproductive health services
. Promote a climate of fear, victimisation and stigmatisation
The amendment Act is necessary to improve women's rights to reproductive health care and choices. Distribution of services remains uneven across provinces, with women, particularly in rural areas, having little or no access. The amendment Act will ensure that access is improved in order for women to exercise their right to choose whether to have an abortion or not.
Issued by the Reproductive Rights Alliance:
Ipas South Africa
Centre for Applied Legal Studies, University of the Witwatersrand Health Systems Trust Women's Health Research Unit, University of Cape Town Women's Legal Centre Mosaic Training, Service & Healing Centre for Women OUT LGBT Well-being Tshwaranang Legal Advocacy Centre to End Violence Against Women Reproductive Health Research Unit, University of Witwatersrand Women's Net
Marion Stevens
Project Manager
Treatment Monitor
Health Systems Trust
PRESS RELEASE:
Reproductive Rights Alliance welcomes adoption of the Choice on Termination of Pregnancy Amendment Act
Today parliament passed the Choice on Termination of Pregnancy Amendment Act. This comes after a process of public hearings undertaken by both houses of parliament. The extended consultation processes came as a result of a Constitutional Court ruling. However, the substance of the law was not in question. In brief, the law is aimed at expediting the designation of facilities; extending the pool of service providers; and clamping down on unscrupulous practitioners.
It builds on the principal Act, the Choice on Termination of Pregnancy Act no 92 of 1996, which has resulted in a positive impact on women's health. In particular it:
. Raised awareness of choices available to pregnant women, enabling
them to discuss options available to them and to access services.
. Significantly reduced the number of women dying by 91% as a result
of backstreet abortions. Also reduced health complications by 50%.
. Reduced public health care costs of treating complications resulting
from backstreet abortion; and
. Provided greater access to services, especially to poor, young and
rural women.
Parliamentary hearings in 2002 identified barriers that prevented optimal access. This resulted in the 2004 Amendment Act that increases and expands access to safe and legal pregnancy terminations, especially for poor and rural women. It does so in the following ways:
. Decentralisation to provinces helps the government improve the
quality of reproductive health services to women, especially at local level.
. It increases the pool of health care providers and the quality of
services.
. It improves provincial administration of reproductive health
services, by enabling better internal accountability (eg. planning, record-keeping, monitoring services etc).
. It prevents the proliferation of illegal abortion clinics and
providers and strengthens the arm of the state in prosecuting these.
Little or no opposition to these provisions was expressed in the public consultation process. The opposition that was voiced was directed at provisions of the principal act (such as conscientious objection) and was aimed at limiting access to services and eroding women's constitutional right to reproductive choices and health-care. Such opposition is well-resourced and is part of a wider, global campaign to attack and erode these rights. It is characterised by strategies that include:
. Repeated and unsuccessful legal challenges to the principal Act;
. Appealing to emotion and the use of graphic materials to stigmatise
termination providers and services, as well as the women who use them;
. The spread of misinformation, including the use of pseudo-science
that draws spurious links between terminations and women's ill health
. Creating a climate of confusion and guilt that intimidates health
workers and clients
For example, the right of health workers to conscientious objection is often raised as a problem. There is no evidence that this requires a legislative response. Despite claims to the contrary, no one has laid a complaint with either Democratic Nursing Organisation of South Africa (DENOSA) or South African Medical Association (SAMA) about being forced to perform TOPs.
The Constitution makes provision for conscientious objection, but also mandates access to reproductive health care and requires non-discrimination.
This provides a framework for genuine issues of conscientious objection to be addressed at management level. However, competency in pregnancy termination care is necessary for all health workers. The Health Professions Council of South Africa (HPCSA) requires doctors to be generalists, able to provide termination of pregnancy for women in various states of life.
Calls for conscientious objection do the following:
. Promote discrimination against patients based on the kind of service
they require
. Disrupt the patient - health worker relationship by prioritising the
rights of the provider over those of the patient
. Marginalise termination services, placing them outside of the core
reproductive health services
. Promote a climate of fear, victimisation and stigmatisation
The amendment Act is necessary to improve women's rights to reproductive health care and choices. Distribution of services remains uneven across provinces, with women, particularly in rural areas, having little or no access. The amendment Act will ensure that access is improved in order for women to exercise their right to choose whether to have an abortion or not.
Issued by the Reproductive Rights Alliance:
Ipas South Africa
Centre for Applied Legal Studies, University of the Witwatersrand Health Systems Trust Women's Health Research Unit, University of Cape Town Women's Legal Centre Mosaic Training, Service & Healing Centre for Women OUT LGBT Well-being Tshwaranang Legal Advocacy Centre to End Violence Against Women Reproductive Health Research Unit, University of Witwatersrand Women's Net
Marion Stevens
Project Manager
Treatment Monitor
Health Systems Trust
Subscribe to:
Posts (Atom)